What the Anion Gap Measures
The anion gap is a useful way to estimate the relationship between tested electrolytes in the blood and the unmeasured ions that also affect acid-base balance. Clinically, it is especially helpful as a quick screen for metabolic acidosis and additional metabolic abnormalities that may not be apparent from a single lab value. An anion gap calculator helps translate routine serum chemistry results into usable diagnostic support at the bedside.
In its simplest form, the anion gap reflects the difference between cationic and negatively charged analytes reported on an electrolyte panel. The major measured components are serum sodium, serum chloride, and serum bicarbonate, with potassium sometimes included depending on the formula used. Because not all ions are directly measured, the gap can uncover patterns that suggest lactic acid accumulation, ketones, retained acids, or ingestion of toxic substances.
From a physiologic perspective, the anion gap is not a diagnosis by itself. It is a screening and analysis tool that helps narrow the differential diagnosis when laboratory results show an abnormal acid-base status. Used well, it supports prompt recognition of serious illness, quicker confirmatory testing, and more targeted bedside assessment.
How to Calculate the Anion Gap
The core calculation formula is straightforward:
Anion gap = sodium - (chloride + bicarbonate)
Certain clinicians and facilities also include potassium in the equation:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Both formulas are used in practice, but the potassium-free version is more common because normal anion gap disorders serum potassium is usually much smaller than sodium and may not meaningfully change interpretation in many cases. Still, if your calculator includes potassium, it is important to know which reference range and formula the tool uses so that the result is interpreted correctly.
To use an anion gap calculator, add the serum values from the patient's lab report:
- Serum sodium Serum chloride Serum bicarbonate Potassium, if the chosen formula includes it
The output should then be compared with the lab's reference range. Reference ranges can differ by analyzer, methodology, and whether potassium is included, so the same numeric result may be interpreted slightly differently across institutions. A useful bedside tool should clearly show the formula and help users interpret the number in context instead of as a stand-alone answer.
As an example: if sodium is 140, chloride is 104, and bicarbonate is 20, the potassium-free anion gap is 16. This may be normal or only mildly elevated depending on the local reference range and albumin level. This is why reading the result matters as much as calculating it.
Adjusting the Anion Gap for Albumin
Albumin is a key unmeasured anion in plasma, so shifts in albumin can significantly affect the apparent gap. In patients with hypoalbuminemia, the measured anion gap may appear falsely normal or only slightly elevated even when clinically important acids are present. For that reason, many clinicians estimate a corrected anion gap to improve sensitivity.
The need for albumin correction is based in serum proteins: when albumin falls, the body loses a important negatively charged component, and chloride may rise to maintain electrical neutrality. That compensation can hide a true high-gap process. In practice, a correction factor is applied to approximate the gap the patient would have if albumin were normal.
A commonly used approach is:
Corrected anion gap = measured anion gap + 2.5 x (4.0 - albumin in g/dL)
This formula is one of various accepted methods, and local practice may vary. The key point is not memorizing a single number but recognizing that low albumin can conceal metabolic acidosis. If the albumin is markedly reduced, corrected interpretation becomes especially important for accurate clinical decision support.
Example: a patient has a measured anion gap of 12 and albumin of 2.0 g/dL. The correction adds 5, resulting in a corrected anion gap of 17. That shift can change the entire diagnostic direction, prompting attention to high-gap causes that might otherwise be missed.
How to Read Elevated, Average, and Decreased Anion Gap Results
Analysis starts with the overall clinical picture, then moves to the numeric result, the adjusted albumin value, and the associated acid-base status. The anion gap is most useful when interpreted with pH, serum bicarbonate, and the rest of the metabolic panel.
High anion gap metabolic acidosis
A high gap usually suggests accumulation of unmeasured acids and points toward high anion gap metabolic acidosis. Common mechanisms include acid production, acid ingestion, or reduced clearance of organic acids. The key bedside question is whether the elevated gap explains the low bicarbonate and whether the patient also has another coexisting process.
A high gap should prompt a focused differential diagnosis, review of symptoms, medication and toxin exposure, and rapid assessment of severity. It may also warrant confirmatory testing such as lactate, ketones, arterial or venous blood gas, renal function testing, and toxicology studies.
Normal anion gap metabolic acidosis
A normal or near-normal result does not exclude metabolic acidosis. Normal anion gap metabolic acidosis often suggests loss of bicarbonate or failure to excrete acid with compensatory chloride retention. In these cases, the acid-base disorder is present even though the gap does not appear elevated. This is why an anion gap calculator should be used as part of a broader interpretation, not as a standalone screening endpoint.
Examples include gastrointestinal bicarbonate loss, renal tubular problems, and other causes of hyperchloremic acidosis. If the clinical setting suggests acidosis but the gap is normal, further analysis of bicarbonate, chloride, potassium, and blood gas values is essential.
Low anion gap
A low anion gap is less common but should not be ignored. It may reflect hypoalbuminemia, analytic issues, excess unmeasured cations, or uncommon paraprotein-related states. In some cases, the low value is an artifact; in others, it is a clue to a real disorder. Because of this, a low result warrants careful review of the laboratory results, albumin, and the possibility of laboratory error before making clinical assumptions.
Overall, sound anion gap interpretation means noting that higher and lower readings can be meaningful and that the result must be interpreted in the setting of the patient’s acid-base disorders, volume status, and other chemistry findings.
Common Causes of an Elevated Anion Gap
A number of disorders are well-known causes of an abnormal gap, particularly when metabolic acidosis is present. The value of the calculator is that it helps identify patterns early and guide the next steps in the diagnostic workup.
Lactic acidosis is one of the most important causes of high-gap acidosis. It can occur with shock, reduced blood flow, severe infection, seizures, hypoxia, and other states of impaired tissue oxygen delivery or utilization. Lactate is an unmeasured anion, so its accumulation can increase the gap substantially.
Ketoacidosis is a further common cause, often seen with diabetes, starvation, alcohol use, or other physiologic stressors. Ketone bodies increase the acid load and raise the anion gap, sometimes with rapid changes over time as treatment begins.
Renal failure can raise the gap because the kidneys are unable to excrete acids effectively. Uremic acids accumulate, and the serum chemistry may show a rising gap alongside worsening creatinine and bicarbonate abnormalities.
Toxic alcohols are critical not to miss. Ingestion of substances such as methanol, ethylene glycol, or related compounds can produce a high-gap metabolic acidosis and severe systemic toxicity. In these situations, the anion gap is part of urgent risk stratification, but it should be paired with confirmatory testing whenever possible.
Additional causes are possible, and mixed presentations are common. That is why the gap should be viewed as a clue rather than a conclusion. It helps narrow the differential diagnosis while further evaluation identifies the exact cause of the metabolic derangement.
Using the Calculator in Clinical Support Decisions
An efficient decision support tool should do more than calculate a number. It should support bedside assessment, minimize arithmetic errors, and help clinicians quickly connect the result with the next best action. In a fast-paced setting, the calculator becomes part of a larger care workflow that starts with lab values and ends with a more informed plan.
In day-to-day practice, the anion gap calculator can help with:
- Prompt screening for high-gap metabolic acidosis Recognition of patterns that suggest lactate, ketones, renal dysfunction, or toxin exposure Correction for albumin when hypoalbuminemia is present Ongoing monitoring across serial lab checks Supporting timely confirmatory testing
Because serum chemistry results are often available before the full clinical picture is clear, the calculator can help prioritize urgency. For example, an elevated corrected anion gap may raise suspicion of a serious metabolic process even before the source is identified. That is especially valuable when the patient is unstable, when bedside history is limited, or when the presentation is nonspecific.
As a bedside tool, the calculator should also lessen cognitive load. A cleanly designed interface turns multiple analytes into a simple output while still showing the underlying formula and correction factor. This promotes more confident interpretation without replacing clinical judgment.
Constraints, Problems, and Recommended Practices
While helpful, the anion gap has significant constraints. First is variability in the reference range. Different laboratories may use different assays or calculation conventions, and the presence or absence of potassium in the formula can alter what counts as normal. Be sure to interpret the result using the same method the calculator uses.
Laboratory error is another frequent pitfall. Erroneous chloride, sodium, or anion gap clinical significance bicarbonate results can distort the gap and create misleading conclusions. If the number does not fit the clinical context, run the test again or review specimen quality before acting on the result alone.
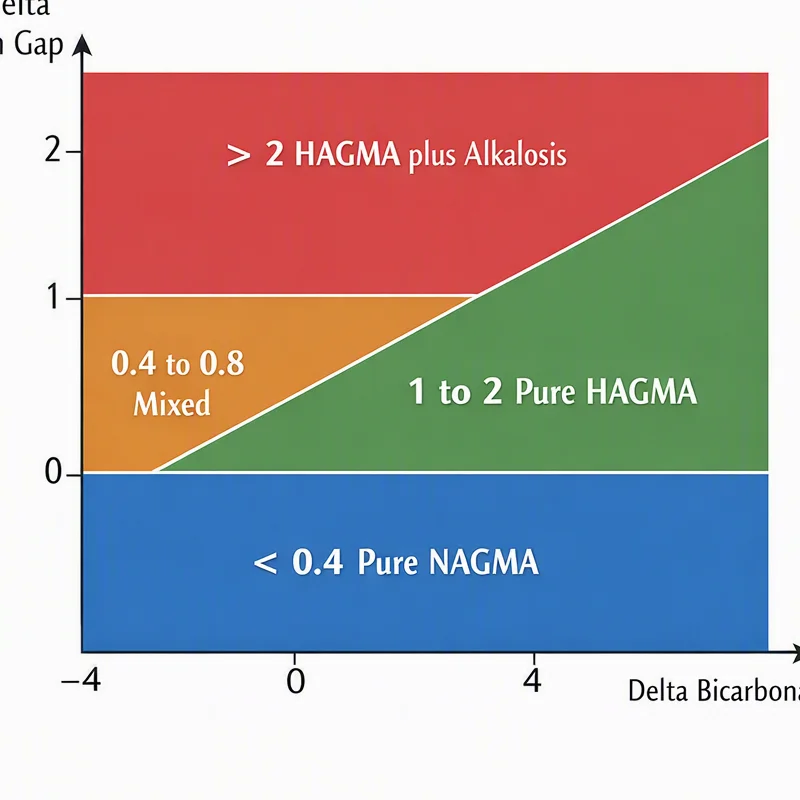
Mixed acid-base disorders can also complicate interpretation. A patient may have a high-gap acidosis and a separate alkalosis, or a normal-gap acidosis plus a second process that masks the expected pattern. In these cases, the anion gap should be interpreted alongside pH, bicarbonate, respiratory compensation, and the overall serum chemistry profile.
Further best practices include:
- Check albumin whenever the gap is unexpectedly normal or low Apply the corrected anion gap when hypoalbuminemia is present Contrast current and prior values to detect change over time Evaluate whether the pattern matches the bedside story Perform confirmatory testing when the abnormal result suggests serious disease
The goal is reliable anion gap interpretation, not just numerical output. A thoughtfully used calculator can enhance screening, support earlier diagnosis, and reduce the chance of missing a clinically important metabolic process.
FAQ
How is calculated the anion gap using sodium, chloride, and bicarbonate?
Use formula anion gap = sodium - (chloride + bicarbonate). Provide the patient’s serum sodium, serum chloride, and serum bicarbonate into the calculator, then contrast the result with the lab’s reference range. Certain formulas also include potassium, so it is important to know which version is being used.
Why must the anion gap be corrected for albumin?
Albumin correction is necessary because albumin is a major unmeasured anion. If albumin is low, the measured gap may underestimate the true acid burden. Correcting for hypoalbuminemia helps uncover a hidden high-gap process and improves the accuracy of clinical interpretation.
What does a high anion gap indicate clinically?
A high value often suggests high anion gap metabolic acidosis from unmeasured acids. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should prompt timely evaluation of the clinical context and consideration of confirmatory testing.
Is it possible for a normal anion gap still occur with metabolic acidosis?
Indeed. Normal anion gap metabolic acidosis is a real disorder and often reflects bicarbonate loss with compensatory chloride retention. A normal result does not rule out metabolic acidosis, so interpretation should include pH, bicarbonate, chloride, and the broader clinical picture.
What are common causes of a low anion gap?
A low anion gap may be caused by hypoalbuminemia, laboratory error, unusual increases in unmeasured cations, or certain protein abnormalities. If the result is unexpected, check the lab data, consider repeat testing, and assess whether albumin or other serum proteins explain the abnormality.