What the anion gap Reflects in Pediatrics
The anion gap is a helpful way to look at the link between key electrolytes in the blood and to get a better sense of acid-base balance. In children, it is often applied as part of a larger review of serum chemistry and test results when a clinician is trying to understand whether there may be an electrolyte imbalance or an acid-base disorder.
Although the anion gap is not a direct measurement of a specific acid, it can work as a clinical clue. It helps clinicians judge whether extra unmeasured acids may be present in the blood. This makes it especially useful in pediatrics, where symptoms such as vomiting, poor intake, breathing changes, or lethargy may be connected to a wider metabolic disturbance.
The concept is simple: the body’s major positively charged and negatively charged particles should stay in a proper relationship. The routinely measured values used in this estimate are sodium, chloride, and bicarbonate. Because these are part of routine serum electrolytes, the anion gap can often be reviewed from a standard blood test without any extra special collection.
In pediatrics, interpretation always depends on the clinical picture. A single anion gap value does not establish illness by itself. Instead, it gives supportive context for the full assessment, including symptoms, hydration status, and other laboratory data.
How an Anion Gap Calculator Works
An Anion Gap Calculator uses a basic calculation formula based on common blood chemistry values. In the most common form, the calculator takes away the measured chloride and bicarbonate from the sodium level:
Anion gap = sodium − (chloride + bicarbonate)
This clear formula gives an anion gap value that can be compared with a reference interval or normal range. The calculation itself is simple, but the clinical interpretation is where pediatric context matters most.
Because the formula uses a sodium level, chloride level, and bicarbonate level, any issue changing those numbers can change the result. For example, dehydration, fluid shifts, or changes in acid production can alter the pattern seen on a chemistry panel. An unexpected result may reflect actual physiology, but it can also reflect a lab measurement problem or another transient factor.
Many calculators are designed to calculate the gap quickly from an electrolyte panel, but they do not take the place of judgment. A calculator can be a quick aid, not a diagnosis. In children, that distinction matters because age, growth, and illness can affect the meaning of the result.
Some tools also allow a correction for albumin, since albumin contributes to the gap and can affect interpretation when it is low. That added step can be helpful when trying to understand whether a result truly reflects an acid-base disturbance or whether low protein levels are changing the reading.
Childhood Typical Values and How It Changes With Age
The normal anion gap in pediatric patients is not always identical to the adult range used by all laboratory. A child reference interval may differ depending on the testing approach, the analyzer, and the local laboratory’s guidelines. This is why a single number should not ever be viewed in isolation alone.
In real-world practice, the most important point is whether the value falls within the lab’s stated normal interval. Even within pediatrics, the reference range may shift slightly with age, growth, and body composition. Younger children may have altered expected chemistry patterns than older children, and newborns have their own separate factors. For this reason, the same anion gap value can have another significance depending on the young patient.
When reviewing a chemistry panel, clinicians look at the full picture: the anion gap, bicarbonate, chloride, sodium, and often albumin. A value that is only mildly beyond the expected interval may be less concerning than one that is clearly abnormal and paired with indications of illness. The result is best understood as part of overall medical interpretation, not as a standalone conclusion.
It is also important to note that a “normal” result does not always rule out a problem. Some children with a real metabolic disturbance may still have a gap that appears normal if the underlying condition is early, mild, or influenced by other factors. Likewise, a borderline value may be less meaningful if the child is otherwise well.
Interpreting a Raised Anion Gap in a Child
A raised anion gap often indicates that excess acids are building up in the body. In a child, this can suggest acidosis, which is a condition where the blood becomes more acidic than expected. The anion gap does not identify the exact cause, but it helps narrow the list of possibilities.
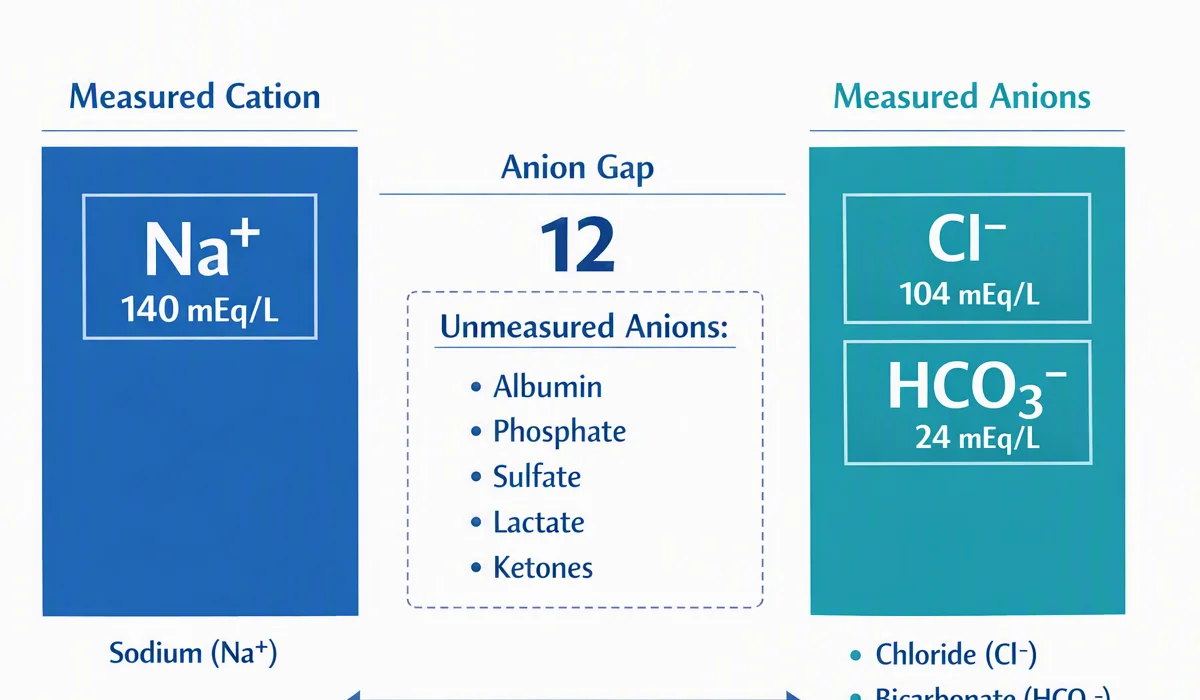
One frequent cause is the buildup of ketones, which can happen when the body is using fat for energy instead of using glucose as usual. This pattern is particularly important in diabetic ketoacidosis, a medical emergency that can occur in children with diabetes. In that situation, the high anion gap may be one of the first laboratory clues that something serious is happening.
Other situations can also raise the gap. Severe illness, poor intake, or abnormal tissue metabolism may result in an acid load that the body cannot quickly clear. In pediatrics, a high value should always be evaluated alongside symptoms such as rapid breathing, vomiting, abdominal pain, confusion, or unusual fatigue.
The value is best understood as a alert rather than a final answer. A child with a high anion gap may need repeat labs, blood glucose testing, or a fuller assessment of acid-base status. The result offers a diagnostic clue, but the cause must be identified through follow-up evaluation.
How to Read a Decreased Anion Gap in a Child
A reduced anion gap is not as common than a higher value, but it can still be important. One major reason is a change in albumin, the main protein in the blood that helps maintain the usual equilibrium of charged particles. If albumin is low, the gap may look lower than expected even when the child is not acutely ill.
A low value can also occur because of laboratory error or another measurement issue affecting the chemistry panel. For that reason, a unexpected result should be reviewed carefully before making conclusions. Repeating the test may be reasonable if the number does not fit the child’s condition or if the sample quality is uncertain.
In some cases, a low anion gap may point to other metabolic or measurement issues. However, in routine pediatric care, the first steps are usually to confirm the result and review albumin, total protein, and the rest of the serum chemistry panel. The main goal is to decide whether the value represents a true physiologic change or an unexpected result caused by testing conditions.
Because a low anion gap is often hard to notice, it should not be ignored if it persists. Even so, it is usually interpreted in the context of the overall clinical picture, not as an isolated diagnosis.
Frequent Causes of Altered Anion Gap Results
Different conditions can alter the anion gap in children. The pattern matters because it can point toward distinct underlying mechanisms affecting serum electrolytes and acid-base balance.
- Dehydration can concentrate blood values and affect how the chemistry panel appears, especially if the child has been losing fluid from vomiting, loose stools, or poor intake. Kidney disease can limit the body’s ability to manage acids and electrolytes, which may lead to a high anion gap or other abnormalities on lab results. Diabetic ketoacidosis is a common cause of high anion gap metabolic acidosis in children and should be treated as an urgent condition. Toxic ingestion of certain substances can affect metabolism or acid handling and may produce a significant acid-base disorder.
These causes do not all present the same way. Certain cases lead to obvious symptoms, while others are first noticed on a blood test ordered for another reason. This is why the anion gap is useful as a screening tool: it may reveal a clue before the full story is clear.
Still, the result is only part of the picture. A child with dehydration may improve quickly with appropriate care, while a child with kidney disease or toxic ingestion may need urgent evaluation. The number alone cannot separate these possibilities.
How to Use Results Safely
This Anion Gap Calculator can be a helpful way to gauge whether a child’s lab values suggest a normal pattern or suspected acid-base imbalance. But safe use means recognizing its limits. The calculator should be paired with the full electrolyte panel, the child’s symptoms, and guidance from a pediatrician or other qualified clinician.
Before drawing conclusions, make sure that the blood test values are current and from a reliable source. Small changes in the sodium, chloride, or bicarbonate levels can change the calculation. If the child is sick, the numbers may change over time, which is why repeat lab results are sometimes necessary.
If the result is abnormal, the next step is usually not to self-diagnose. Instead, it may lead to a focused medical review, which can include checking blood glucose, ketones, kidney function, hydration status, and sometimes a more detailed acid-base assessment. This is especially important when the child has symptoms such as confusion, fast breathing, severe vomiting, or reduced alertness.
Parents and caregivers should think of the calculator as a screening aid that helps organize information. It can support questions like, “Does this chemistry panel fit with a metabolic problem?” or “Is there a reason to ask for a follow-up evaluation?” That approach is much safer than using the number by itself to make decisions.
If a child has concerning symptoms, the best action is to contact a clinician promptly. A calculator can help interpret context, but it cannot replace medical judgment, physical examination, or a full review of the blood test.
Common Questions About Anion Gap in Children
What is an anion gap calculator used for in children?
An anion gap calculator is used to determine the anion gap from standard blood chemistry values such as sodium, chloride, and bicarbonate. In children, it helps screen for possible electrolyte imbalance or acid-base disorder and may provide a useful diagnostic clue when reviewing lab results. urine AG quick calculator It does not diagnose a specific illness on its own.
What is a normal anion gap range for children?
The normal range is determined by the laboratory’s pediatric reference range and the testing method used. Children may have mildly different reference values than adults, so the lab’s stated interval should always be used for interpretation. A result should be reviewed in context with the full serum chemistry panel and the child’s symptoms.
What causes a high anion gap in a child?
A high anion gap can occur when extra acids build up in the body, leading to metabolic acidosis. Common causes include diabetic ketoacidosis, kidney disease, critical illness, and some forms of toxic ingestion. Ketones are an especially important clue when the body is relying on fat for energy instead of glucose.
Can a low anion gap be serious in children?
A low anion gap is often not as urgent than a high one, but it can still matter. It may be related to low albumin, a testing issue, or in uncommon cases another medical problem. Because laboratory error can also cause an unexpected result, repeat testing or follow-up review may be needed if the number does not align with the clinical picture.
Should parents rely on an anion gap calculator without a doctor?
No. Anion Gap Calculator should not replace a pediatrician or other clinician. It can help estimate a value from a blood test, but interpretation requires supportive context, including the child’s symptoms, other lab values, and the broader clinical situation. It is a screening tool, not a diagnosis.