What Is the Anion Gap?
The anion gap is a calculated value based on common electrolytes in a serum chemistry panel. It helps clinicians evaluate acid-base balance and identify types of acid-base disorders, especially when assessing possible metabolic acidosis. Although it is not a directly measured result, it reflects the difference between major positively charged and negatively charged particles in blood chemistry.
In practical terms, the anion gap helps estimate the balance between unmeasured anions and unmeasured cations. A change in this balance can signal an underlying electrolyte imbalance, a metabolic derangement, or a specific disease process that needs further medical evaluation. Because it uses routine serum electrolytes, it is a useful diagnostic tool in everyday care.
The anion gap is often interpreted alongside the basic metabolic panel and sometimes with blood gas analysis to understand a patient’s acid-base status. It is best thought of as a laboratory assessment that supports clinical judgment rather than replacing it. In that sense, it serves as a risk indicator for certain conditions and a guide to next steps in the diagnostic evaluation.
Anion Gap Calculation Formula
The usual anion gap calculation formula is as follows:
Anion gap = sodium - (chloride + bicarbonate)
In this calculation, sodium is the primary measured cation, while chloride and bicarbonate are the principal measured anions. The result estimates the amount of anion concentration not directly measured in routine testing.
Several laboratories may use slightly different calculation methods. Some include potassium, though most clinical formulas do not. Because the details can vary, the reference interval or reference range may also differ depending on the laboratory and the assay used.
The formula is simple, but the clinical interpretation is more complex. A above-normal value can point toward high anion gap metabolic acidosis, while a below-normal value may suggest a measurement issue, protein abnormality, or a shift in electrolyte balance. This is why the formula is only the starting point for clinical interpretation.
In what way the Anion Gap Calculator Functions
An Anion Gap Calculator automates the formula and enables users to rapidly handle input values for sodium, chloride, and bicarbonate. After the measured electrolytes are entered, the calculator performs the arithmetic and presents the calculation result.
Many calculator tools are created to cut down on manual errors and speed up the review of test results. That makes them especially helpful during a busy medical evaluation, when quick pattern recognition is important. The calculator can also support a more structured interpretation guide for clinicians and students studying how to identify abnormal patterns.
An effective calculator does more than simply output a number. It can help users compare the result with a reference range, determine whether serum albumin may be affecting the result, and work through the possibility of a corrected value. Therefore, the calculator becomes part of a broader laboratory assessment and not just a math tool.
For example, if the sodium level is 140, chloride is 102, and bicarbonate is 24, the formula would give an anion gap of 14. Whether that is normal depends on the lab’s reference range and the clinical context. This illustrates why the Anion Gap Calculator should be used with the patient’s full picture in mind.
Normal Anion Gap Range
The normal anion gap is not consistent across all laboratories because different methods and measurement systems affect the reference range. In many settings, the interval is based on the lab’s own test values and assay characteristics. For that reason, the most accurate comparison is always to the specific reporting lab’s listed range.
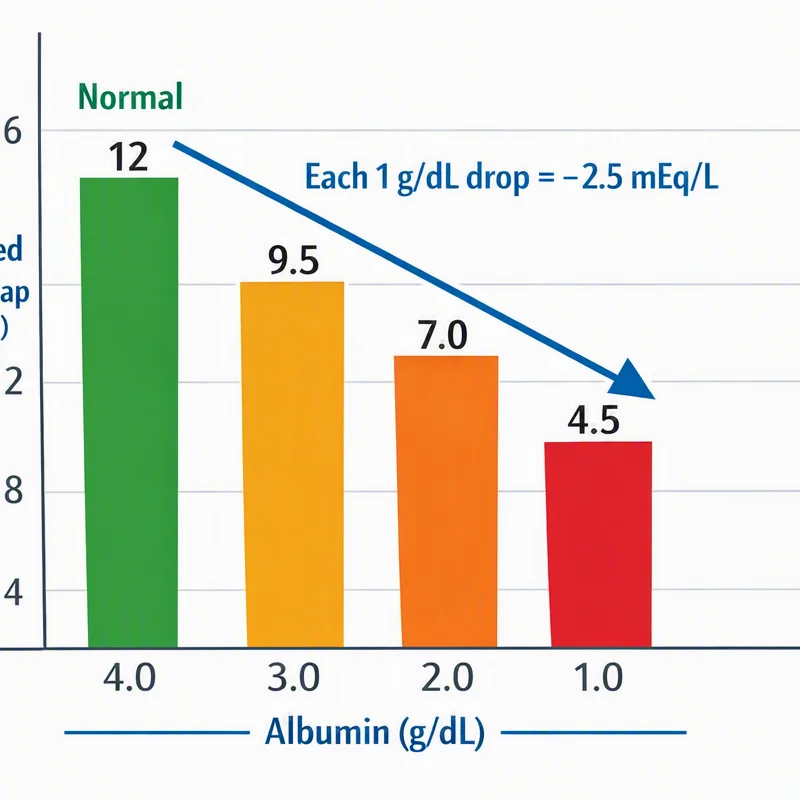
Albumin plays a major role in shaping the observed gap because it is an important unmeasured anion. If serum albumin is low, the apparent gap may also be lower than expected even when other processes are present. This is why a single number should not be interpreted in isolation.
Understanding the normal range https://anion-gap-calculation.com/causes/normal.html is essential for identifying whether a result reflects a true physiologic change or simply normal variation. The goal is not to memorize one universal cutoff, but to interpret the result against the proper reference range and the patient’s overall condition.
When reviewing anion gap values, clinicians look for consistency across the patient’s electrolyte status, symptoms, and other labs. The number becomes more meaningful when paired with acid-base status, serum chemistry trends, and the broader clinical picture.
High Anion Gap Causes
A high anion gap may indicate the presence of extra acids in the body and is a key clue in high anion gap metabolic acidosis. This pattern shows the accumulation of unmeasured acids that consume bicarbonate while leaving the gap widened. In many cases, this is one of the most useful ways to narrow the differential diagnosis of metabolic acidosis.
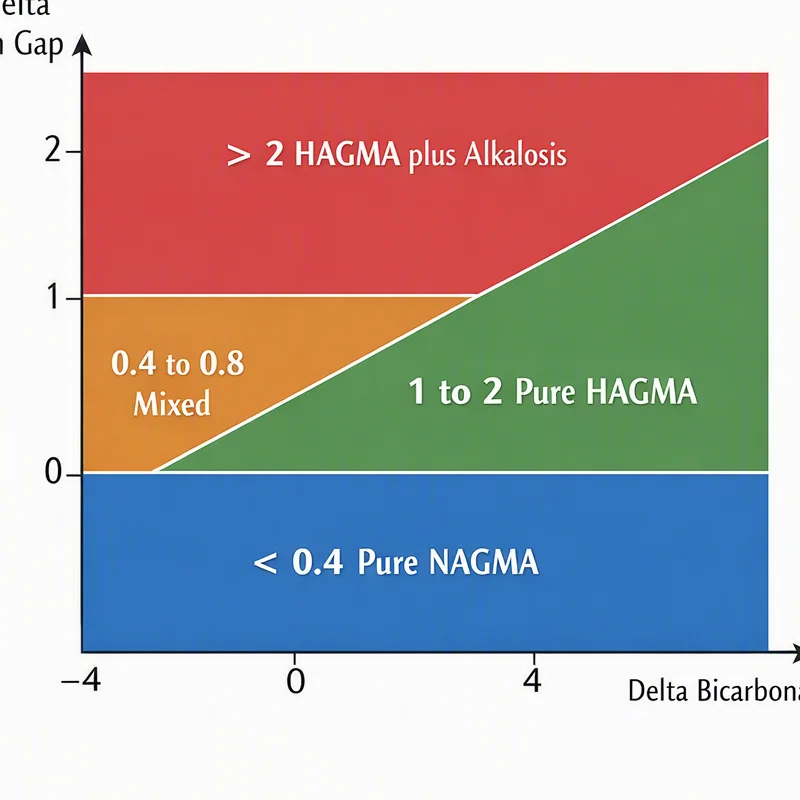
Frequent causes include lactic acidosis, ketoacidosis, and uremia. Lactic acidosis may develop when tissues are underperfused or under oxygen stress. Ketoacidosis is often seen with insulin deficiency or prolonged starvation states. Uremia results from reduced kidney function and the buildup of acid-related waste products.
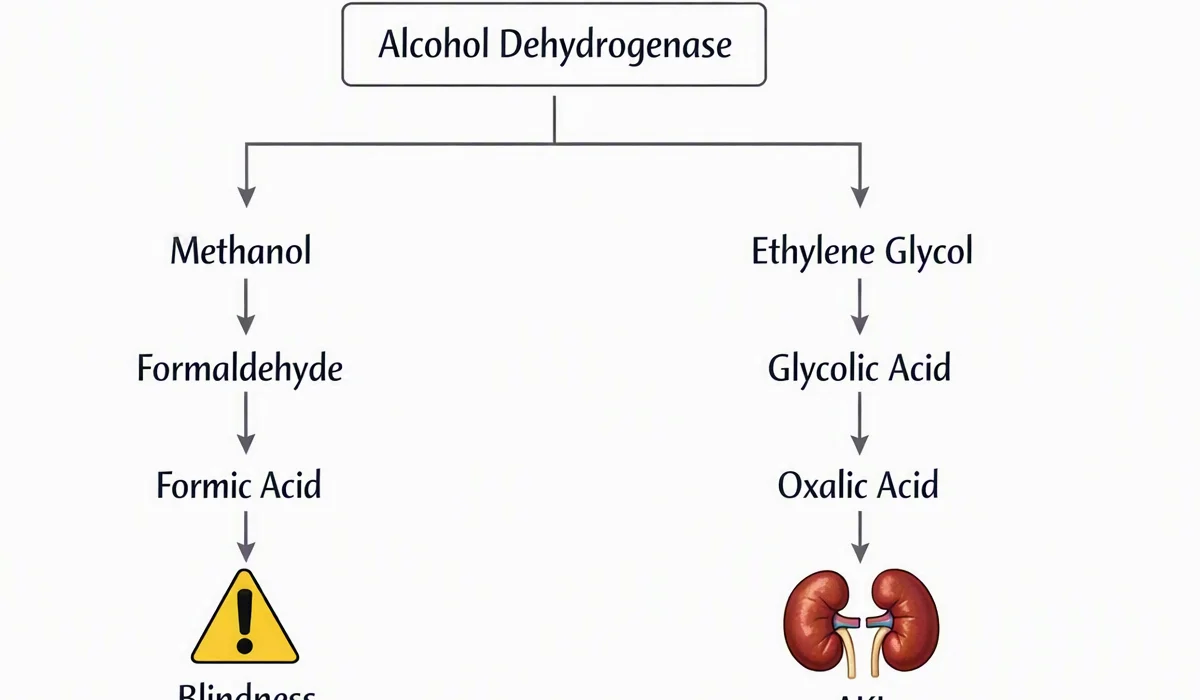
Other factors may involve toxic ingestions and severe metabolic disruption, but the core idea remains the same: the gap rises because there are a greater number of unmeasured anions than expected. This keeps the anion gap a valuable diagnostic tool for identifying a specific type of acid-base disorder.
When a high result appears, clinicians often combine it with blood gas analysis and the basic metabolic panel to confirm the pattern and determine severity. A high result is not itself a diagnosis; it is a signpost that directs the diagnostic evaluation toward the likely cause.
Low Anion Gap Causes
A low anion gap is rarer than a high one, but it can still be important clinically. One of the leading explanations is hypoalbuminemia, because low albumin reduces the contribution of unmeasured anions. Without enough albumin, the calculated difference may decrease even if other aspects of acid-base physiology remain abnormal.
Another notable cause is multiple myeloma, where abnormal proteins can alter the balance of charged particles in the blood. In such cases, the low gap may be a clue to an underlying plasma cell disorder that requires further medical evaluation. Although not every low value points to a serious illness, it should not be ignored without proper interpretation.
Lab error is also a key consideration. A specimen problem, instrument issue, or reporting mistake can produce an unexpectedly low result. Because of that, repeating the test and reviewing the underlying serum electrolytes is often wise when the value does not fit the clinical picture.
In rarer cases, shifts in electrolyte balance or changes in unmeasured cations can contribute. The key is to consider the low value as part of a broader assessment rather than a stand-alone finding.
Corrected Anion Gap and Albumin Adjustment
The adjusted anion gap recalculates the raw result for the influence of serum albumin. This albumin adjustment matters because albumin is a major contributor to the body’s overall anionic charge and substantially affects the calculated gap. If albumin is low, the uncorrected number can underestimate the true acid burden.
Using a corrected value improves acid-base analysis, especially when assessing complex cases of metabolic acidosis. It helps clinicians reduce the risk of missing an elevated gap that is masked by hypoalbuminemia. In other words, the corrected version often gives a clearer picture of the patient’s actual acid-base state.
The correction approach changes by method, but the principle is consistent: adjust the observed gap based on albumin concentration and then interpret the revised number against the appropriate normal range. This brings precision to the overall clinical assessment and can change how urgently a result is pursued.
Whenever albumin is significantly reduced, it is important to interpret the anion gap cautiously. A apparently normal uncorrected result may still mask a clinically important disorder, so the corrected anion gap can be a better reflection of the patient’s true metabolic state.
Typical Pitfalls While Using the Method
One recurring problem is measurement error. Minor errors in sodium, chloride, or bicarbonate can shift the final value enough to change interpretation. This is especially relevant when the result is close to the upper or lower edge of the reference range.
Another common issue involves electrolyte units. A calculator or user must be sure the values are entered in the same units specified by the formula and the lab report. Even simple formatting mistakes can lead to a misleading calculation result.
Another key point is not to overlook related analytes such as ionized calcium and magnesium. While they are not part of the basic formula, abnormal levels can affect the body's overall balance and shape the broader interpretation. These factors can influence how a clinician thinks about the patient’s blood chemistry.
Finally, users sometimes forget that the anion gap is a supportive measure, not a complete diagnosis. It should be considered alongside symptoms, the basic metabolic panel, and other findings. Overreliance on the number alone can lead to missed context and weaker clinical judgment.
When to Consider the Anion Gap in Clinical Practice
The anion gap is most useful when evaluating metabolic acidosis, especially if the cause is not immediately obvious. It helps separate common patterns of acid-base disturbance and guides next steps in the diagnostic evaluation. In this setting, it functions as a practical marker of electrolyte imbalance and a possible clue to serious illness.
Clinicians often order or review it with a blood gas analysis to better understand acid-base status. The combination of blood gas findings, the basic metabolic panel, and the gap calculation provides a fuller picture than any single test. This makes the result more valuable in real-world medical evaluation.
It is additionally helpful when monitoring changes over time. A changing gap may suggest improvement or deterioration of an underlying metabolic derangement. In this way, it can serve as a valuable risk indicator and surveillance tool.
Because the result depends on several measured values, it can be especially informative when the diagnosis is uncertain. It helps clinicians recognize whether the issue is likely a elevated-gap process, a low-gap pattern, or something affected by lab error or altered protein levels. That makes it a practical component of routine laboratory assessment.
Frequently Asked Questions
What is the formula for calculating the anion gap?
The most common formula is sodium - (chloride + bicarbonate). It uses the measured electrolytes from a chemistry panel to calculate the difference between unmeasured anions and unmeasured cations.
What is a normal anion gap value?
The normal range depends on the laboratory’s reference range and measurement method. Because laboratory values can vary, the best comparison is the range listed with the patient’s report.
What causes a high anion gap?
A high anion gap is commonly caused by high anion gap metabolic acidosis, including lactic acidosis, ketoacidosis, and uremia. These conditions raise unmeasured acids and increase the gap.
Why is albumin correction important in the anion gap?
Albumin correction matters because serum albumin is a major unmeasured anion. If albumin is low, the uncorrected result may obscure a clinically important disorder, so the corrected anion gap gives better acid-base interpretation.
Can a low anion gap be a sign of a serious condition?
Yes, a low anion gap can sometimes reflect hypoalbuminemia, multiple myeloma, or lab error. While it is not always dangerous, it deserves review because it may point to a serious underlying problem.