What Anion Gap Means and Why It’s Important
The anion gap is a calculated value from a routine electrolytes panel that helps medical professionals evaluate acid-base balance. It is not a directly measured test; instead, it is derived from widely reported serum chemistry values. Because it shows the relationship between measured cations and measured anions, the anion gap can act as a useful diagnostic aid when evaluating an acid-base disorder.
In basic terms, the anion gap helps estimate the amount of unmeasured anions in the blood. When those unmeasured anions rise, the result may point toward metabolic acidosis, especially high anion gap metabolic acidosis. That makes the anion gap helpful for interpretation of a laboratory result, especially when paired with the rest of the patient’s clinical picture.
The term “gap” can be confusing because it does not represent a physical gap. It is a numeric difference that compares sodium against chloride and bicarbonate. This difference helps clinicians identify whether an underlying metabolic derangement is present and whether the cause may involve acids, toxins, kidney function, or changes in proteins. In that sense, the anion gap is a preliminary tool, not a final diagnosis.
The value is affected by the balance of unmeasured cations and unmeasured anions, as well as by albumin and other proteins. Because of that, a single number should never be interpreted in isolation. Good patient assessment requires looking at symptoms, history, and other lab data together with the anion gap value.
Using an Anion Gap Calculator
An anion gap calculator is a convenient way to perform the calculation quickly and accurately. Most calculators use three values from the electrolyte panel: serum sodium, serum chloride, and serum bicarbonate. After those values are entered, the calculator produces the anion gap value and may contrast it with a normal range or normal range.
The standard calculation formula is:
Anion gap = Serum sodium − (Serum chloride + Serum bicarbonate)This formula reflects the relationship between measured ions in the blood. Sodium is the main measured cation, while chloride and bicarbonate are the primary measured anions used in the formula. The result is a practical estimate of the space left by other charged particles in the serum chemistry panel.
To use the calculator properly, enter the values exactly as reported by the laboratory. Small differences in units, rounding, or transcription can alter the anion gap value. The calculator is best used when used as part of https://anion-gap-lookup821.evergrovio.com/posts/is-fluid-loss-impacting-the-anion-gap a broader workflow: verify the numbers, calculate the gap, compare it with the reference range, then read the result in clinical context.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation would be 140 − (102 + 24) = 14. That result may fit within some normal ranges, but the interpretation still depends on the laboratory’s reference interval and the patient’s overall condition.
Because the anion gap calculator is a diagnostic aid rather than a complete answer, it should be used alongside other information such as pH, bicarbonate trend, lactate, ketones, renal markers, and medication history. This approach enhances the clinical significance of the result and minimizes overreliance on a single number.
Anion Gap Reference Range
The reference range for the anion gap varies by laboratory method, devices, and result-reporting conventions. In general, the normal range is often considered to be approximately around the low teens, but the exact number should always be taken from the laboratory’s stated reference interval. That is especially relevant because different instruments can give slightly different results.
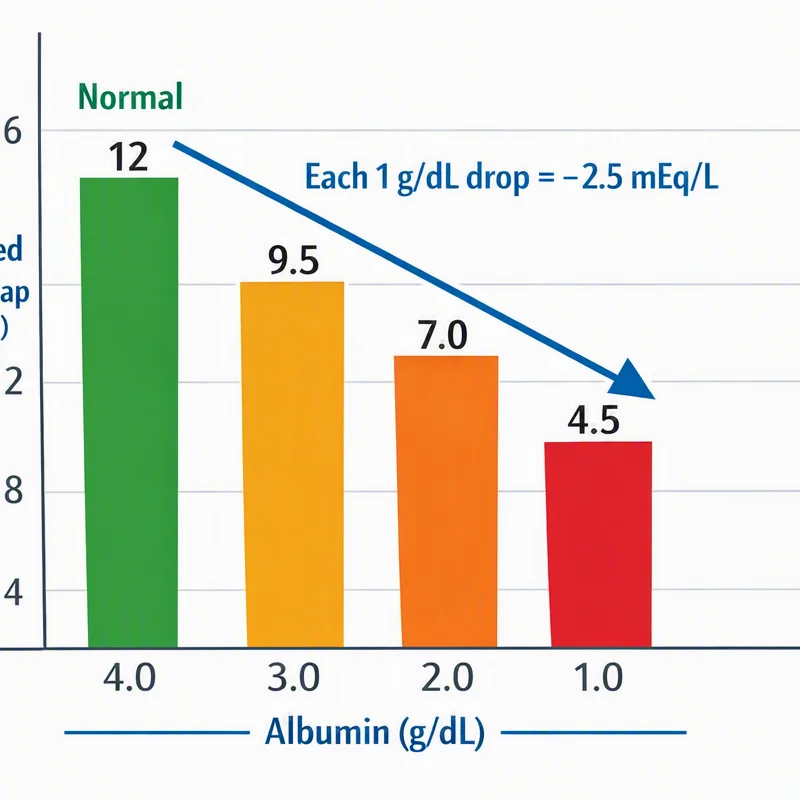
Albumin has a major effect on the anion gap because it is a negatively charged protein. Lower albumin levels usually lower the anion gap, which means a result that appears “normal” may actually be misleading if albumin is reduced. For that reason, the reported value should be reviewed with the albumin level whenever possible.
Lab variation is another important reason not to use a universal cutoff without context. A normal range in one laboratory may not correspond to another laboratory’s range, even when both are correct. The best practice is to interpret the anion gap using the local reference interval provided with the test result.
A useful way to think about the anion gap is as a reference interval rather than a strict pass-or-fail threshold. Values above the normal range may indicate excess unmeasured acids, while values below the range may reflect low albumin, paraproteins, or other conditions. Either way, the number becomes meaningful only when tied to the patient’s symptoms and the rest of the electrolyte panel.
When the reported value is borderline, repeat testing or checking the broader clinical picture may be more helpful than making a conclusion from a single laboratory result. A slightly elevated or slightly low value can be real, but it can also result from method differences, specimen issues, or a simple transcription error.
How to Read a High Anion Gap
A elevated anion gap usually suggests the presence of more acids in the blood, which can be a sign of acid-base imbalance. The classic pattern is elevated anion gap metabolic acidosis, where the bicarbonate is consumed as acid builds up and the calculated gap rises. In this setting, the anion gap becomes a marker to the underlying differential diagnosis.
One common cause is lactate buildup, which occurs when lactate accumulates due to poor oxygen delivery, shock, seizures, severe illness, or impaired clearance. Another important cause is ketoacidosis, which can occur with diabetes, prolonged fasting, alcohol use, or other metabolic states that promote ketone production.
Kidney failure can also increase the anion gap because the kidneys cannot eliminate acid effectively. As kidney function declines, unmeasured acids build up, and the laboratory result may show this metabolic pattern. In these cases, the anion gap is one piece of a larger picture that includes creatinine, blood urea nitrogen, urine findings, and symptoms.
High values can also point to toxin exposure, medication effects, or less common metabolic states. The key clinical question is not just whether the number is high, but why it is high. That is why the anion gap is best treated as a screening tool that helps narrow the differential diagnosis rather than as a final diagnosis by itself.
When a high value is found, it is often useful to confirm the bicarbonate level, look for acidemia, and assess the patient for common triggers. The pattern of the laboratory result can help guide next steps, especially when paired with lactate, ketones, renal function, and a careful history.
How to Interpret a Decreased Anion Gap
A decreased anion gap is rarer than a high value, but it can still be medically significant. One of the leading causes is hypoalbuminemia, because a decrease in albumin lowers the amount of negative-charge protein in the serum. This change can decrease the apparent gap even when the patient does not have a real acid-base problem.
Another significant cause is paraproteinemia, in which abnormal proteins may shift the balance of measured and unmeasured ions. In some cases, the presence of excess positively charged proteins can drive the calculated result lower than expected. This is why a low value should not be dismissed automatically.
Lab error is also a common explanation for a markedly low or below-zero result. Specimen contamination, instrument issues, or transcription mistakes can all alter the calculation. If the value does not match the clinical picture, repeating the test and reviewing the original electrolyte panel is a sensible first step.
Other causes may include unusual electrolyte patterns, medication-related effects, or analytical interference. Because low values are often due to nonpathologic factors, the most useful approach is to verify the data, check the albumin level, and consider whether abnormal proteins or technical issues might explain the result.
A low anion gap can be a valuable clue when it is real, but it should be read carefully. The most useful response is to compare the number with the laboratory reference interval, verify the calculation, and ask whether the result matches the patient’s clinical presentation.
Correcting the Anion Gap for Albumin
Albumin correction is important because albumin is one of the main unmeasured anions in the blood. When serum albumin is low, the measured anion gap may miss the true extent of acid accumulation. In those situations, a corrected anion gap can provide a better interpretation.
The rationale for albumin correction is driven by protein binding and the charge carried by albumin in plasma. Since albumin contributes negative sites, a reduction in albumin decreases the gap even when acid-base balance is abnormal. Correcting for albumin helps compensate for that effect by applying a correction factor tied to the albumin level.
Different clinical references use distinct correction approaches, but the general idea is unchanged: adjust the anion gap upward when albumin is below normal. This is especially useful in acutely ill patients, where hypoalbuminemia is common and can mask high anion gap metabolic acidosis.
Using a corrected anion gap can shift the assessment in a meaningful way. A value that looks normal on the uncorrected calculation may become elevated after albumin correction, uncovering hidden acid accumulation. That can improve clinical significance and inform further testing or treatment.
For practical patient assessment, the best workflow is to review the measured anion gap first, then examine the albumin level, then decide whether albumin correction is appropriate. If the corrected result differs notably from the uncorrected one, that difference may be diagnostically important.
Typical Causes, Pitfalls, and Patient Context
Interpreting the anion gap requires more than calculating a number. The result should always be considered alongside symptoms, exam findings, and the broader laboratory pattern. One reason is that the same value can mean different things depending on whether the patient has respiratory symptoms, dehydration, kidney disease, ingestion risk, or known diabetes.
Various important causes of high results deserve special attention. Toxic alcohols can produce high anion gap metabolic acidosis after ingestion, and salicylates can create complex acid-base findings that may include an elevated gap. These are critical diagnoses because they can require urgent treatment and specific testing.
Kidney disease is another important context because reduced acid excretion may increase the anion gap over time. Depending on severity, the pattern may reflect chronic retention of acids or an acute worsening of renal function. That is why renal markers and clinical status should be reviewed whenever the gap is abnormal.
Medication effects can also influence the result. Some drugs promote acidosis, some alter electrolyte handling, and some interfere with laboratory measurements. The medication list should therefore be part of every interpretation.
Common pitfalls include assuming every high result is dangerous, ignoring albumin, and forgetting to verify the original electrolyte values. Another pitfall is failing to consider the entire acid-base disorder. A patient may have mixed disorders, in which the anion gap is only one part of the story.
The most useful approach is a practical workflow: confirm the electrolyte panel, calculate the value, compare it with the reference range, adjust for albumin if needed, and then use the clinical context to anion gap clinical significance guide the differential diagnosis. That process turns the calculator into a real decision-support tool rather than a standalone number generator.
FAQ
What does an anion gap calculator do?
An anion gap calculator is used to rapidly determine the anion gap from serum electrolytes and assist in interpreting acid-base balance. It is a basic tool that helps evaluate metabolic acidosis, especially when checking for a high anion gap metabolic acidosis pattern.
What is the usual anion gap reference range?
The reference range is determined by the laboratory method and the reporting system. The normal range is often in the teens, but the correct value to use is the laboratory’s own reference interval. Interpret always the result using the range shown with the test.
Why might the anion gap be elevated?
A high result can occur when there are extra acids in the blood. Common causes include lactic acidosis, ketoacidosis, and renal failure. Toxic alcohols and salicylates are also key possibilities depending on the clinical context.
Why might the anion gap be decreased?
A low result is often due to hypoalbuminemia, because albumin is a major unmeasured anion. Other causes include paraproteinemia and lab error. If the number seems unexpected, it should be checked again and interpreted with the full electrolyte panel.
Should the anion gap be corrected for albumin?
Yes, in many cases it should. Albumin correction can reveal a more reliable corrected anion gap, especially when serum albumin is low. This matters because albumin affects the measured gap through protein binding and can otherwise mask a clinically important acid-base disorder.