Understanding the Anion Gap?
The anion gap is a computed value used to help assess acid-base equilibrium and detect certain causes of metabolic acidosis. It compares the main measured cations and anions in a basic electrolyte panel, commonly using sodium, chloride, and bicarbonate. Because not all ions are directly measured, the anion gap helps estimate the amount of unmeasured anions in the blood.
Clinically, the anion gap is a valuable diagnostic tool for detecting an acid-base disorder. A change in the measured anion gap can point to a metabolic derangement such as high anion gap metabolic acidosis or, in some cases, normal anion gap metabolic acidosis. The result must always be read in context with the full electrolyte panel and other laboratory values.
At its core, the anion gap reflects electrochemical stability. If there are extra unmeasured acids in the blood, the gap can go up. If the balance is altered by changes in albumin or other proteins, the gap may appear reduced than expected even when clinically important abnormalities are present.
Why Albumin Counts in the Anion Gap
Albumin is the most abundant protein in plasma and acts as a major protein anion. Because it has a negative charge, albumin significantly affects the measured anion gap. When serum albumin is low, the anion gap may be artificially lowered even though unmeasured anions are still present.
This is why hypoalbuminemia matters. Low albumin can obscure a significant acid-base disorder by lowering the measured anion gap. In practical terms, a patient with low albumin may have a “normal” gap that is actually abnormal after correction. This is where albumin correction becomes important for precise clinical interpretation.
Albumin correction refines lab interpretation by accounting for the reduced negative charge from low albumin. Without adjustment, clinicians may overlook the presence of unmeasured anions and miss an important clue to metabolic acidosis. The corrected value gives a clearer picture of the patient’s acid-base status.
Albumin-Based Anion Gap Equation
The most commonly used correction formula adjusts the measured anion gap based on the serum albumin level. One common version is:
Albumin-corrected anion gap = the observed anion gap + 2.5 × (4.0 − serum albumin in g/dL)
The formula uses a reference albumin of 4.0 g/dL. For every 1 g/dL decline in serum albumin below 4.0, the corrected value goes up by about 2.5 mEq/L. That correction helps return the corrected value closer to what it would be with normal protein anion contribution.
The reference interval for the normal anion gap can vary slightly depending on the laboratory, analyzer, and method used. For this reason, the correction formula should be interpreted alongside local reference range information and the patient’s broader clinical picture.
Some institutions use slightly different albumin correction approaches, but the goal is the same: approximate the true gap calculation after accounting for low albumin. The corrected anion gap is especially helpful when evaluating acidemia and suspected high anion gap metabolic acidosis.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator simplifies the procedure by automatically combining sodium, chloride, bicarbonate, and albumin to deliver both the measured anion gap and the corrected anion gap. This is especially useful when multiple laboratory values need to be assessed quickly and consistently.
To use an anion gap calculator, enter the key components from the electrolyte panel:
- Sodium level Chloride value Bicarbonate level Serum albumin reading, if albumin correction is needed
The calculator at first performs the gap calculation using the standard anion gap formula, then applies albumin correction if needed. This helps change the measured anion gap into a corrected value that better reflects ion balance and unmeasured anions.
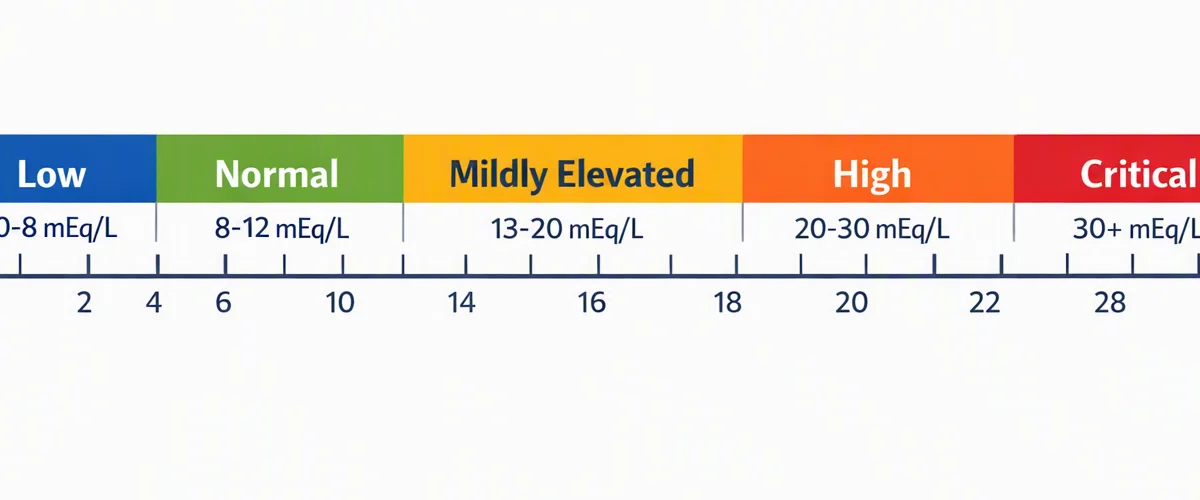
For example, if the serum albumin is low, the anion gap calculator can show whether a seemingly normal result is actually elevated after adjustment. That makes it a valuable tool for clinical interpretation, especially in patients with complex acid-base disorder patterns.
Detailed Computational Example
This is a basic illustrative example using standard lab values. Consider the laboratory values are:
- Sodium: 140 mEq/L Chloride: 104 mEq/L Bicarbonate: 20 mEq/L Serum albumin: 2.5 g/dL
First, calculate the observed anion gap:
Anion gap = sodium − (chloride + bicarbonate)
Applying the values above:
140 − (104 + 20) = 140 − 124 = 16 mEq/L
Afterward, apply the compensation formula for albumin:
Corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin)
Insert the serum albumin value:
Corrected anion gap = 16 + 2.5 × (4.0 − 2.5)
Corrected anion gap = 16 + 2.5 × 1.5 = 16 + 3.75 = 19.75 mEq/L
This worked example shows how decreased albumin can obscure a more significant gap. The measured anion gap was already somewhat elevated, but the corrected value is even higher and more clearly suggests a high anion gap metabolic acidosis pattern. A calculator or formula-based approach minimizes error and increases consistency during lab interpretation.
How to Interpret a Corrected Anion Gap
Assessing the corrected anion gap starts with the standard range or lab interval used by the lab. When albumin correction is applied, the corrected value should be compared with that reference range rather than the unadjusted number alone.
A elevated anion gap after correction implies that unmeasured anions are present and that a high anion gap metabolic acidosis may be present. Frequent acid-base disorders in this category include lactic acidosis, ketoacidosis, and renal failure-related acidosis. The corrected result is especially helpful when serum albumin is low because the measured anion gap may otherwise downplay the severity of the disturbance.
A normal corrected value may mean that the apparent elevation was mainly due to baseline variation or that the clinical issue lies elsewhere. In some cases, a patient may have normal anion gap metabolic acidosis instead, meaning bicarbonate loss is offset by chloride retention rather than accumulation of unmeasured acids. That distinction is important for clinical interpretation and treatment planning.
Remember that the corrected value is not a diagnosis by itself. It is part of the overall assessment of acid-base balance, which includes symptoms, medication history, kidney function, and the full set of laboratory values.
Common Sources of an High Anion Gap
Many states can raise the anion gap by adding to unmeasured anions. Of the most important are lactic acidosis, ketoacidosis, and renal failure. These issues often lead to metabolic acidosis with a high anion gap and can progress quickly if not recognized.
Lactic acidosis occurs when lactate accumulates due to poor tissue oxygen delivery, shock, severe infection, seizures, or other metabolic stress. The excess lactate contributes to acid accumulation and decreases bicarbonate.
Ketoacidosis is commonly seen in uncontrolled diabetes, prolonged fasting, or heavy alcohol use. Ketone bodies act as unmeasured anions and widen the gap calculation.
Renal failure can elevate the anion gap because the kidneys are unable to clear organic acids effectively. As acid builds up, bicarbonate falls and the measured anion gap rises.
Further causes may include toxins, medications, or mixed metabolic conditions. Because the corrected anion gap reflects both the measured anion gap and albumin correction, it can aid in determine whether the apparent abnormality is genuine or partly due to low albumin.
Restrictions and Clinical Considerations
Although valuable, the anion gap has major limitations. Laboratory variation can influence the result, especially when different analyzers or measurement methods are used. That is why the same patient may have somewhat different results across settings. The reference interval should always be interpreted in context with the local laboratory method.
Combined disorders can also complicate interpretation. A patient may have more than one acid-base disorder at the same time, such as metabolic acidosis combined with vomiting or respiratory changes. In those cases, the corrected anion gap may more clearly reveal hidden pathology, but it still must be interpreted with the full clinical picture.
Another key issue is electrolyte imbalance. Shifts in sodium, chloride, or bicarbonate can affect the measured anion gap and make the result less straightforward. A low albumin state may further distort the picture, so albumin correction is helpful but not perfect.
The best approach is to view the corrected anion gap as one part of comprehensive lab interpretation. It is a useful diagnostic tool, but it does not replace clinical judgment, repeat testing when needed, or evaluation of the underlying cause of acid-base disorder.
FAQ
What is the formula for albumin-corrected anion gap?
A commonly used correction formula is: corrected anion gap = measured anion gap + 2.5 × (4.0 Click for more − serum albumin in g/dL). This adjusts the measured value for low albumin and helps estimate the true gap calculation more accurately.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major protein anion. When serum albumin is low, the measured anion gap can appear falsely normal or low. Albumin correction improves clinical interpretation by accounting for this missing negative charge.
What is the normal anion gap range?
The normal anion gap range depends on the laboratory and the analyzer used, so the reference range may vary. Many labs provide their own reference interval, and that local range should guide interpretation rather than a single universal number.
What is the effect of low albumin affect the anion gap?
Low albumin decreases the measured anion gap because there are fewer negative protein anions in the blood. This can obscure a true increase in unmeasured anions and make a high anion gap metabolic acidosis seem less obvious than it actually is.
When should an anion gap calculator be used?
An Anion Gap Calculator should be used when you want a rapid, accurate way to evaluate an electrolyte panel, especially when serum albumin is low or acid-base balance is unclear. It is particularly helpful in suspected metabolic acidosis, when corrected value analysis can enhance lab interpretation and assist the assessment of acid-base disorders.