What Is the Anion Gap and How Is It Computed?
The anion gap is a calculated value that aids clinicians interpret acid-base status from a standard serum chemistry panel. It is calculated from electrolytes and is typically based on the measured concentrations of sodium, chloride, and bicarbonate. In simple terms, it gauges the difference between the main measured cations and anions in blood.
The classic formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some labs add potassium, but potassium is often omitted because its concentration is comparatively minor compared with sodium. https://anion-gap-tracker244.cavandoragh.org/how-to-interpret-an-anion-gap-calculator-in-renal-failure Even though the calculation is straightforward, the result can provide an important diagnostic clue about an underlying electrolyte imbalance, changes in unmeasured ions, or an unexpected finding related to plasma proteins.
A normal result supports a normal acid-base balance, while a high or low result can point toward a broader differential diagnosis. Because interpretation depends on the lab’s methods and analyzer, the reference interval may differ a little from one institution to another.
How an Anion Gap Calculator Operates
An Anion Gap Calculator handles the math using the numbers entered for Na, chloride, and bicarbonate, and in some cases potassium. This helps make easier to interpret a lab result quickly and consistently. The calculator does not diagnose disease by itself, but it can aid identify a trend that deserves closer attention.
Because the anion gap is calculated from a routine electrolyte panel, the calculation is only as sound as the input values. If the bicarbonate value is inaccurate, or if sodium and chloride are affected by a preanalytic or analytic issue, the computed gap may be inaccurate. That is why clinicians often rule out artifact before assigning too much clinical significance to a single number.
An Anion Gap Calculator is especially helpful when the value is outside the usual reference range. A narrowed anion gap or low anion gap may point to low albumin, excess positively charged proteins, or a testing issue. In practice, the calculator supports identification of a pattern, but the final interpretation depends on the overall clinical picture and whether the value makes sense in context.
What’s Paraproteinemia?
Paraproteinemia refers to the existence of an abnormal paraprotein in the blood, typically produced by a one clone of plasma cells. It is a type of monoclonal gammopathy, indicating one clone makes a large amount of one specific immunoglobulin or part of an immunoglobulin, such as a light chain.
Such proteins can be detected because they differ from the polyclonal mixture of normal antibodies. According to the condition, the paraprotein may be intact immunoglobulin, free light chains, or another abnormal protein product. Some patients have no symptoms at first, while others develop signs related to organ injury or blood viscosity.
The most common disease associated with paraproteinemia is multiple myeloma, but not all monoclonal gammopathy is malignant. Some cases are discovered incidentally during laboratory testing done for other reasons. Because the paraprotein can change how blood chemistry values read, it may show up as a protein abnormality that alters the anion gap.
Can Abnormal paraprotein levels Decrease the Anion Gap?
Absolutely. Paraproteinemia can reduce the anion gap, and a low anion gap may be an valuable clue to the presence of a paraprotein-related disorder. The key reason is that some paraproteins are positively charged proteins at normal body pH. When these proteins circulate in sufficiently high amounts, they act as cationic paraproteins and shift the balance of measured and unmeasured ions.
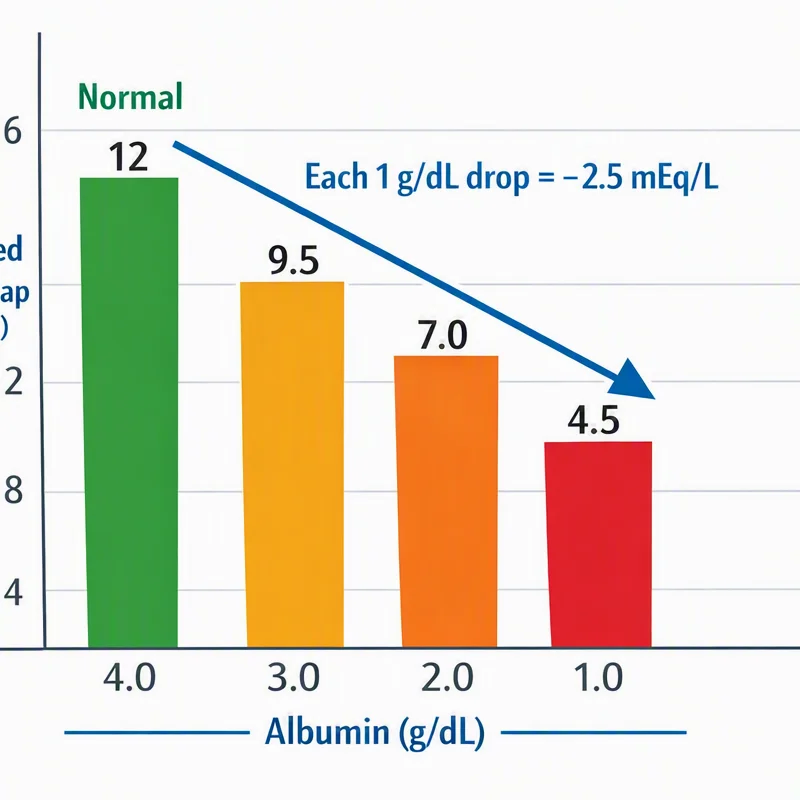
In many cases, the decrease is slight. The anion gap may be only modestly decreased, not necessarily absent. Still, when a low gap appears on an Anion Gap Calculator and the result is not explained by other factors, paraproteinemia becomes part of the differential diagnosis.
This relationship is clinically helpful because the anion gap is not a screening test for paraproteinemia by itself, but it can be a hint that prompts further evaluation. In some patients with multiple myeloma, the low anion gap is one of the initial abnormal chemistry findings, especially when combined with anemia, renal dysfunction, or elevated total protein.
That said, a low anion gap is not diagnostic. Many other factors can lower it, and a normal gap does not exclude paraproteinemia. The result should be interpreted alongside albumin, total protein, and other laboratory data.
Underlying Mechanisms of a Reduced Anion Gap in Paraproteinemia
Multiple processes can help explain why paraproteinemia lowers the anion gap. The key is the presence of cationic paraproteins. These proteins contribute unmeasured positive charge to plasma, which must be balanced by shifts in measured ions such as chloride. As chloride rises to preserve electroneutrality, the calculated anion gap falls.
Hypoalbuminemia often contributes as well. Albumin is a major unmeasured anion, so when albumin is low, the anion gap decreases. In a patient with paraproteinemia, low albumin can enhance the effect and make the gap look even lower. This is why clinicians often correct for albumin when interpreting the result.
Protein binding also matters. Abnormal plasma proteins can modify how ions move in the bloodstream and can alter the measured relationship between sodium, chloride, and bicarbonate. In some cases, the paraprotein itself may affect assay behavior or distort the chemistry profile through lab interference.
These mechanisms do not all operate the same way in every patient. The specific immunoglobulin class, concentration, and charge properties of the paraprotein all influence the final chemistry pattern. That is why paraproteinemia can be associated with a narrowed anion gap in one case and a seemingly normal value in another.
Other Common Sources of a Decreased Anion Gap
Paraproteinemia is an key cause of a low gap, but it is not the most frequent one. Before assuming a plasma cell disorder, clinicians should consider other explanations, especially laboratory error. A sample mix-up, contamination, instrument issue, or specimen handling problem can create an abnormal result that disappears on repeat testing.
Electrolyte abnormalities can also decrease the anion gap. Hypercalcemia can contribute because excess calcium adds unmeasured cations. Hypermagnesemia can do the same. Another classic cause is lithium, which is a positively charged ion that may reduce the calculated gap when present in sufficient concentration.
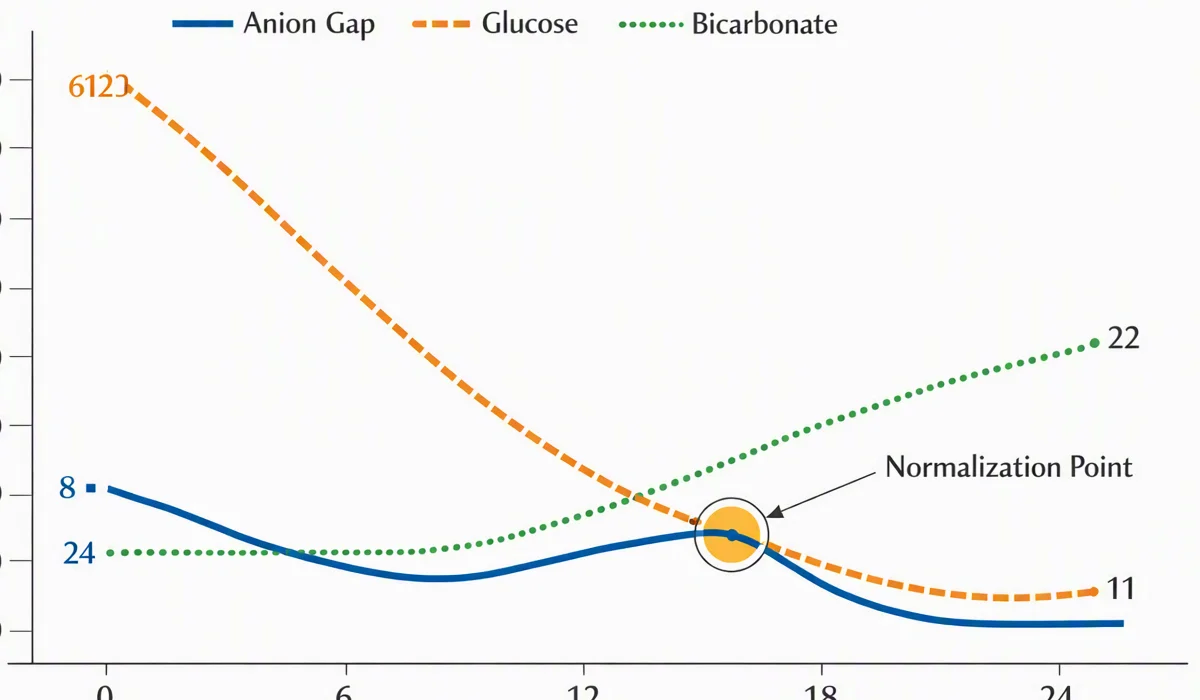
Low albumin remains one of the most frequent non-artifact reasons for a decreased result. Since albumin is a major unmeasured anion, hypoalbuminemia can produce a low gap even without paraproteinemia. That is why the albumin level should always be reviewed with the chemistry panel.
Because several causes overlap, a low result should not be treated as diagnostic on its own. It is better viewed as a signal to rule out artifact, review the medication list, assess albumin, and consider whether a protein disorder is plausible.
When a Low Anion Gap Should Prompt Additional Testing
A low gap deserves careful attention when it is ongoing, unexplained, or accompanied by other abnormalities. In those situations, the next step often includes repeat testing to confirm that the result is real. Rechecking the chemistry panel can help distinguish a one-time issue from a reproducible finding.
If the low gap persists and albumin does not explain it, the clinician may order serum protein electrophoresis to look for a monoclonal spike or other abnormal protein pattern. This is a key screening test for paraproteinemia. If the electrophoresis is abnormal or suspicion remains high, immunofixation can identify the specific immunoglobulin type.
Free light chains are also useful, especially when the paraprotein is not easily visible on electrophoresis. Light-chain disease can be missed if only total protein or routine electrophoresis is reviewed. Together, these tests help characterize the protein abnormality and determine whether it fits a benign or malignant process.
The decision to investigate further should be guided by the entire clinical picture, not just the Anion Gap Calculator output. A low anion gap plus anemia, kidney dysfunction, bone symptoms, or elevated total protein is more concerning than an isolated borderline abnormality.
Clinical Clues That Indicate Paraproteinemia
Several findings can make paraproteinemia more probable. Anemia is frequent because marrow function may be affected or because chronic disease is present. Renal dysfunction can occur when monoclonal proteins damage the kidneys or contribute to light-chain deposition. These clues are often more informative than the low anion gap alone.
Bone pain is an additional classic feature, especially when plasma cell disorders weaken bone structure. Patients may describe continuous pain, tenderness, or fractures with minimal trauma. In the setting of a protein abnormality, this symptom raises concern for multiple myeloma.
Hyperviscosity may appear when large amounts of paraprotein increase blood thickness and impair circulation. Symptoms can include headache, visual changes, dizziness, or bleeding tendency. Although less common, it is an important sign of clinically significant paraproteinemia.
Additional clues include elevated total protein, low albumin, recurrent infections, neuropathy, or an unexplained change in kidney function. When several of these features appear together, the low anion gap becomes a more useful diagnostic clue rather than an isolated laboratory curiosity.
Common Questions About Paraproteinemia and the Anion Gap
Can paraproteinemia lower the anion gap?
Yes. Paraproteinemia can lower the anion gap, especially when the paraprotein is a positively charged protein. The effect may be modest, but a low anion gap can be a valuable clue that prompts further evaluation for a monoclonal gammopathy.
Why does multiple myeloma sometimes cause a low anion gap?
Multiple myeloma can produce large amounts of monoclonal immunoglobulin or light chains. Some of these proteins behave as cationic paraproteins, which lowers the calculated anion gap. Low albumin in myeloma can lower it further.
Can a reduced anion gap be attributed to laboratory error instead of disease?
Absolutely. Laboratory error is a typical reason for an surprising low result. For this reason repeat testing is often suggested before pursuing an thorough workup. If the value returns to normal, artifact becomes more probable than disease.
Should albumin be checked when the anion gap is low?
Absolutely. Albumin should be checked because hypoalbuminemia is one of the leading reasons for a low anion gap. Because albumin is a major unmeasured anion, a low value can help explain the finding or make paraproteinemia appear more pronounced.
What tests confirm paraproteinemia after a low anion gap?
Typical confirmatory tests include serum protein electrophoresis, immunofixation, and free light chains. These studies help find and define the abnormal protein, determine whether a monoclonal gammopathy is present, and direct further evaluation.