What propylene glycol exposure is and where it is found
Propylene glycol is a solvent and carrier utilized in a number of medical and nonmedical products. In clinical environments, it is most important because it can appear in IV medications, especially certain sedatives and other formulations that need a liquid base. It can also be present in some oral products and topical products. Most exposures are harmless, but large or prolonged exposure can create a toxicity problem, especially in hospitalized patients.
This matters since propylene glycol is not just an ingredient; it is a compound that is metabolized by the body into other substances. Under the right conditions, those metabolites can affect acid-base balance and lead to abnormal serum chemistry findings. In some patients, the clinical picture includes high anion gap findings, especially when the exposure is significant or renal clearance is impaired.
From a diagnostic assessment standpoint, propylene glycol exposure is often overlooked unless the medication list is reviewed closely. That is why laboratory interpretation must be paired with clinical correlation. The product source, route of exposure, and duration all influence whether propylene glycol becomes clinically relevant.
How the anion gap is determined
The anion gap is a computed value used to assist in identifying certain forms of metabolic acidosis. It represents the gap between observed cations and measured anions in the blood. The usual anion gap formula uses serum sodium, serum chloride, and serum bicarbonate.
A streamlined version is:
anion gap = serum sodium − (serum chloride + serum bicarbonate)An anion gap calculator performs this calculation and can help clinicians and patients understand whether the result falls in a normal interval or suggests an acid-base problem. Because the result relies on the measured electrolyte values, even small electrolyte variations can change the number.
The anion gap is important because unmeasured anions can increase in the blood during conditions such as lactic acidosis, ketoacidosis, or toxin ingestion. When interpreting the number, clinicians also consider albumin, since low albumin can decrease the measured gap and hide a clinically important abnormality. That is why the albumin-corrected anion gap is often more useful than the unadjusted result.
How propylene glycol can raise the anion gap
Yes, propylene glycol can lead to a high anion gap in the setting of propylene glycol toxicity. The mechanism is usually indirect rather than instant. After exposure, propylene glycol is converted into acidic compounds, including organic acids, which can promote high anion gap metabolic acidosis. In addition, the body may develop a coexisting lactic acidosis, which additionally increases the gap.
Another important clue is the osmolar gap. Propylene glycol itself increases serum osmolarity, so early toxicity may present with an high osmolar gap before the anion gap rises. As metabolism continues, the parent compound falls while acidic metabolites collect, shifting the pattern from isolated osmolar gap elevation to a combined osmolar gap and high anion gap presentation.
This progression is why the timing of testing matters. A patient may initially have a high osmolar gap and later show increasing acidosis, elevated lactate, and a rising anion gap. In other words, propylene glycol can be part of a mixed laboratory pattern that evolves over time.
Common causes of high anion gap metabolic acidosis
Propylene glycol is just one possible cause of metabolic acidosis. A wide differential diagnosis is crucial whenever the anion gap is elevated. Typical causes include ketoacidosis, lactic acidosis, renal failure, and exposure to toxic alcohols. All of these can produce a similar lab pattern, but the underlying mechanism is different.
Ketoacidosis is often seen with diabetes, starvation, or prolonged vomiting, while lactic acidosis may occur with shock, sepsis, hypoperfusion, or certain drugs and toxins. Renal failure can raise the gap because the kidneys cannot clear acid effectively, allowing unmeasured acids to accumulate. Toxic alcohols, such as methanol or ethylene glycol, can also produce an elevated anion gap and osmolar gap pattern.
That is why laboratory interpretation should not rely on a single number alone. The anion gap calculator can identify a concerning result, but the final diagnosis depends on the clinical context, medication exposure, and additional testing.
Indicators and signs of propylene glycol toxicity
The symptoms of propylene glycol toxicity can be unclear at first. Patients may develop altered mental status, hypotension, and tachypnea as the acid-base imbalance worsens. Tachypnea often suggests respiratory compensation for acidosis. Some patients may also exhibit signs of reduced perfusion or sedation, depending on the total exposure and the drugs involved.
A rising serum lactate can be an key clue, especially when the clinical picture suggests an unexplained acid-base problem. Elevated lactate does not prove propylene glycol as the cause, but it increases suspicion when combined with medication exposure, abnormal serum chemistry, and a high anion gap. Because the signs overlap with other illnesses, clinical correlation is important.
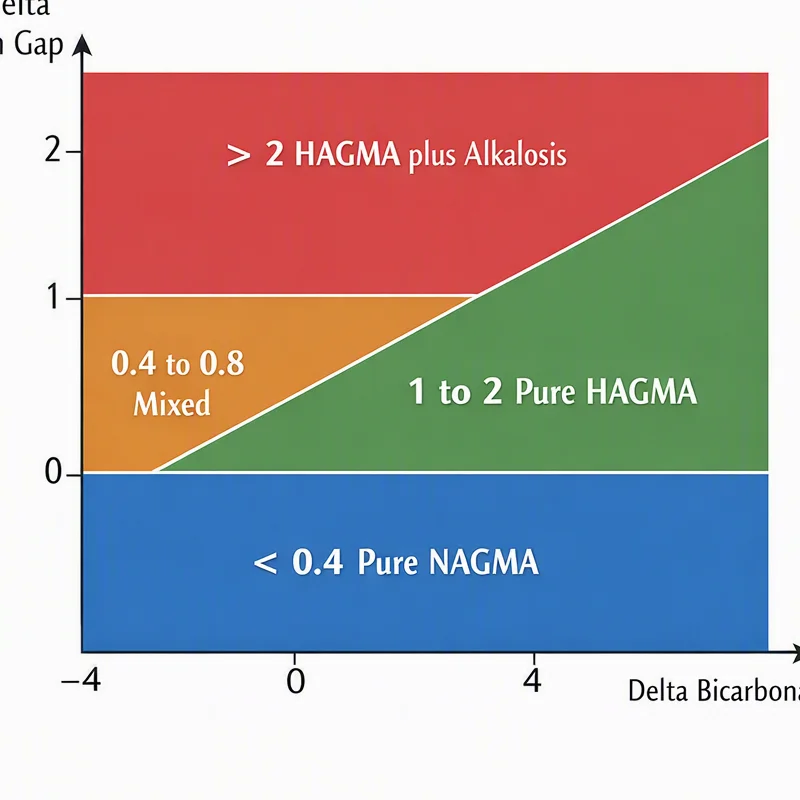
Severe cases can worsen rapidly, particularly when the patient has reduced clearance or multiple risk factors. A careful review of medications, infusion history, and serial labs is often the quickest way to recognize the problem.
Laboratory tests for assessing possible toxicity
If propylene glycol intoxication is suspected, the assessment usually includes serum osmolality, determination of the osmolar gap, a blood gas, and evaluation of renal function. These measures help determine whether the patient has a combined toxic and metabolic pattern.
Serum osmolality is compared with the calculated osmolarity to identify an osmolar gap. A widened gap suggests unmeasured osmotically active substances, which may include propylene glycol or other toxic alcohols. The blood gas helps define the severity of the acid-base disorder and shows whether the patient has metabolic acidosis with respiratory compensation. Renal function testing is important because reduced clearance can worsen toxicity and prolong exposure.
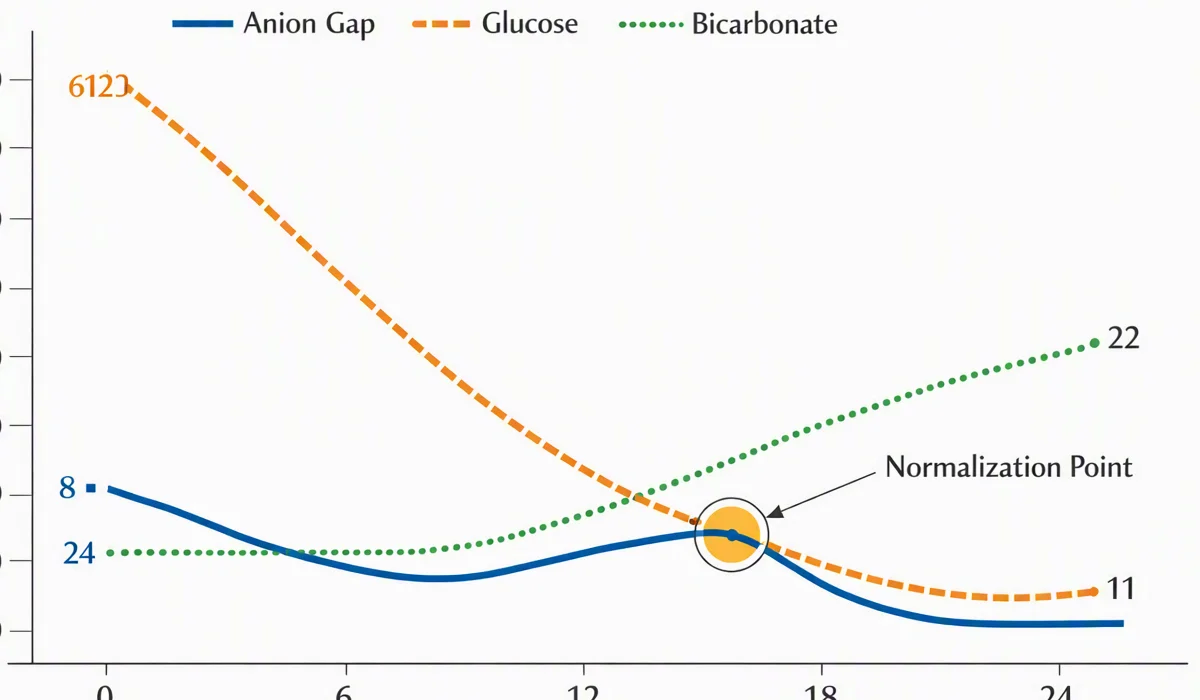
Additional labs often include serum lactate, electrolytes, and repeat chemistry panels. Serial testing can show whether the anion gap is rising or resolving after intervention. In many patients, the pattern of serum chemistry abnormalities provides the strongest evidence before specialized toxin levels are available.
How to understand an Anion Gap Calculator output
An anion gap calculator is valuable, but the result should carefully be interpreted in context. To begin, determine whether the value is in the normal range for the facility used. Normal ranges can vary slightly depending on the analyzer and whether potassium is included in the formula. A value that is borderline in one lab may be obviously abnormal in another.
Then, evaluate the possibility of hypoalbuminemia. As albumin is a major unmeasured anion, low albumin can hide a true acidosis. An albumin-corrected anion gap gives a more accurate estimate of the underlying acid burden when albumin is reduced. This adjustment is particularly helpful in critically ill patients, where albumin is often low.
Finally, ask whether the result matches the overall picture. A high anion gap with normal lactate and normal ketones may suggest a toxin, while a high gap with elevated lactate may suggest tissue hypoperfusion, sepsis, or propylene glycol toxicity. Good interpretation depends on clinical context, not just the number.
When propylene glycol exposure becomes dangerous
Danger grows with dose-dependent toxicity, extended exposure, and limited ability to eliminate the compound. This is especially relevant with some benzodiazepines and other intravenous medications that use propylene glycol as a solvent. Continuous or high-dose infusion can lead to accumulation over time.
Renal impairment raises risk because the kidneys have a key role in clearing the compound and its byproducts. If renal clearance is reduced, propylene glycol and its metabolites may accumulate, leading to osmolar gap elevation, lactic acidosis, and high anion gap metabolic acidosis.
Risk peaks when multiple factors stack together: high medication dose, prolonged infusion, critical illness, dehydration, and impaired kidney function. In that setting, monitoring should be more regular and clinicians should stay highly alert for toxicity.
Treatment and management of suspected propylene glycol toxicity
The first step in management is discontinuation of the suspected source. Discontinuing the offending medication or exposure can prevent further accumulation. Depending on the severity of the case, the patient may also need supportive care, including fluid resuscitation, correction of electrolyte abnormalities, and treatment of acidosis.
Monitoring is important after the exposure is stopped. Serial serum chemistry testing, blood gas assessment, serum lactate, and renal function checks help show whether the acid-base disorder is resolving. If the patient has severe symptoms, rapidly worsening acidosis, or significant renal dysfunction, intensified treatment may be needed.
Hemodialysis can be considered in severe cases because it helps remove propylene glycol and correct associated metabolic derangements. It may be especially useful when there is significant acidosis, hemodynamic instability, or impaired renal clearance. The decision is based on the full clinical picture rather than the anion gap alone.
When to require prompt medical evaluation
Urgent evaluation is advised if there are emergency symptoms such as progressive confusion, severe weakness, breathing difficulty, collapse, or signs of shock. A patient with suspected toxic exposure and a suddenly worsening condition should not wait for routine follow-up.
Concerning features include severe acidosis, markedly low bicarbonate, ongoing low blood pressure, or rapidly increasing lactate. These findings may signal a severe acid-base disorder that needs urgent treatment. If propylene glycol exposure is possible, a timely medical assessment can identify whether the patient needs hospital monitoring, medication changes, or hemodialysis.
Since this condition can overlap with other causes of high anion gap metabolic acidosis, clinicians should evaluate the full clinical picture early. Early review of medication exposure, serum osmolality, blood gas results, and renal function can prevent delays in care.
Frequently asked questions about propylene glycol and the anion gap
Can propylene glycol cause a high anion gap?
Yes, it can. Propylene glycol can cause a high anion gap, especially when exposure is substantial or prolonged. It may https://anion-gap-formula557.nexorafield.com/posts/what-s-the-expected-anion-gap-in-pediatrics first raise the osmolar gap and then, as it is metabolized into acidic metabolites, contribute to high anion gap metabolic acidosis and lactic acidosis.
What is the difference between an anion gap and an osmolar gap?
The anion gap represents unmeasured charged particles and helps recognize causes of metabolic acidosis. The osmolar gap shows the difference between measured and calculated osmolarity and suggests unmeasured dissolved substances, such as propylene glycol or other toxic alcohols. Both are important, but they answer different questions.
Which medications contain propylene glycol?
Propylene glycol can be found in some intravenous medications, including certain benzodiazepines, sedatives, and other formulations that use it as a solvent. It may also appear in some oral products and topical products. The exact formulation depends on the drug and manufacturer, so the medication list should be examined closely.
What symptoms may indicate propylene glycol toxicity?
Possible manifestations include altered mental status, hypotension, tachypnea, and evidence of worsening acidosis. A rising serum lactate may also be present. Since these findings are not specific, they must be interpreted with history of exposure, lab findings, and general clinical correlation.
How is propylene glycol toxicity treated?
Therapy usually starts with discontinuation of the source and supportive care. Clinicians observe the patient closely with repeat labs, including blood gas, serum chemistry, and renal function. In serious cases, hemodialysis may be used to eliminate the toxin and correct severe acidosis.