What Is the Anion Gap and Why Does It Matter So Much in Shock?
The anion gap is a practical way to look for hidden acids in the blood and to help sort out causes of metabolic acidosis during shock. In clinical practice, it is part of a larger acid-base interpretation that starts with the electrolytes in a standard serum chemistry panel. When tissue oxygen delivery drops, the body may shift toward anaerobic pathways and produce acid, making the anion gap a useful diagnostic clue in undifferentiated shock.
In shock, the anion gap is important because it can point toward a perfusion problem, a toxic exposure, or another secondary cause of metabolic derangement. A rising gap often suggests unmeasured anions are accumulating, while a normal gap may indicate bicarbonate loss or a different acid-base disorder. Either way, the number should be interpreted in the context of hemodynamic instability, resuscitation status, and the rest of the clinical assessment.
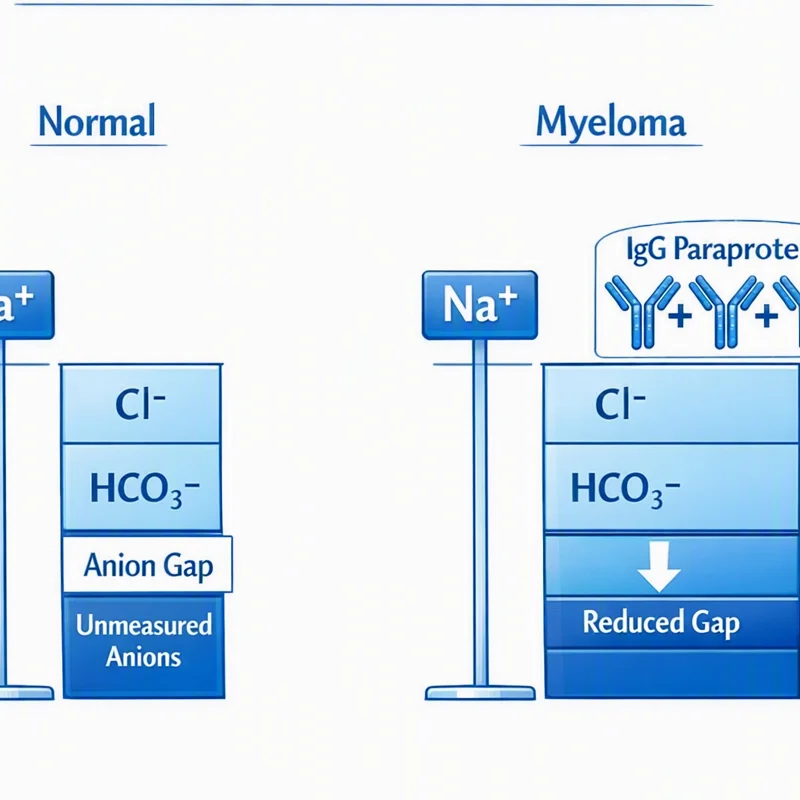
A useful way to think about the anion gap is as a laboratory marker that narrows the differential. It does not diagnose shock by itself, but it can help identify whether the acid-base disorder is more consistent with lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or another process. In critical care, that distinction can alter the next step quickly.
How to Apply an Anion Gap Calculator Correctly
An anion gap calculator is no better than the results entered into it. The formula usually depends on serum sodium, serum chloride, and serum bicarbonate, which are obtained from the electrolyte panel. Because the output can influence urgent decisions, the numbers should be checked for agreement with the broader serum chemistry and the clinical picture.
Most calculators use a standard formula that compares measured cations and anions. If the result seems surprising, first verify the lab values and confirm whether the bicarbonate is from the chemistry panel rather than a blood gas. Even small changes in chloride or bicarbonate can shift interpretation, especially in a patient with evolving shock and ongoing resuscitation.
To use the calculator correctly, consider these steps:
- Confirm the electrolyte panel is recent and not outdated. Use the same set of values from one blood draw when possible. Check whether albumin is decreased, since that can mask a real gap. Compare the result with the arterial blood gas and lactate. Interpret the number as part of acid-base assessment, not in isolation.
The anion gap calculator is especially helpful when the clinical question is whether the patient’s acidosis suggests unmeasured acids or another pattern. In shock, this can aid rapid bedside reasoning, but it should never replace clinical assessment or trend monitoring.
What Does a High Anion Gap Suggest in Shock?
A high anion gap in circulatory collapse usually points to accumulation of acids or toxins. The primary cause in unstable patients is lactic acidosis, which often reflects tissue hypoperfusion. When circulation and oxygenation are inadequate, cells shift to anaerobic metabolism, generating lactate and driving the gap upward.
This pattern is common in sepsis, hemorrhage, cardiogenic shock, and other states with impaired perfusion. The anion gap serves as a helpful diagnostic clue because it may rise before the clinical picture fully declares itself. In a patient with metabolic acidosis and hemodynamic instability, a high gap should raise concern for ongoing oxygen debt and inadequate resuscitation.
That said, a high anion gap does not automatically mean the cause is lactate. It only indicates that unmeasured acids are present. The next step is to match the lab pattern with the story: infection, hypoperfusion, renal dysfunction, diabetic decompensation, or ingestion. In critical care, the value is strongest when combined with the arterial blood gas, lactate, and bedside findings.
In shock, a rising anion gap often signals worsening perfusion deficit, but the cause still needs targeted identification.
How Do You Differentiate High Anion Gap Acidosis Causes?
After a high gap is found, the primary aim is to identify the underlying secondary cause. In shock, the top causes include ketoacidosis, kidney failure, toxic alcohol exposure, and salicylates. Each follows a different treatment path, so the pattern on the labs and the history matter.
Ketoacidosis can happen in diabetes, starvation, or alcohol-related states and often presents with an elevated gap plus low serum bicarbonate. Renal insufficiency can also produce a high gap because acid clearance is impaired. With toxic alcohol exposure, the gap may be high early, sometimes before an osmolar gap closes in, and the patient may have neurologic findings or unexplained acidosis. Salicylates can cause a mixed acid-base disorder, often combining respiratory alkalosis with metabolic acidosis.
Helpful clues for telling them apart include:
- A history of diabetes, fasting, or alcohol use for ketoacidosis Known renal disease, oliguria, or increasing creatinine for renal failure History of exposure, altered mentation, or vision changes for toxic alcohols Ringing in the ears, hyperventilation, or mixed respiratory findings for salicylates
During shock, these causes may overlap with lactic acidosis. For example, a septic patient with renal dysfunction can have more than one acid-base disorder at once. This is why the high anion gap should always trigger broader diagnostic reasoning rather than a single-track conclusion.
What Means a Expected Anion Gap Suggest in Shock?
A typical anion gap does not rule out significant acidosis in shock. It may point to normal anion gap metabolic acidosis, which often results from bicarbonate loss rather than build-up of unmeasured acids. In the unstable patient, this can occur with loose stools, renal tubular acidosis, or chloride-heavy fluid administration causing hyperchloremia.
A normal anion gap acidosis is important because it can coexist with shock-related hypoperfusion. For example, a patient may have received substantial chloride-containing fluids during resuscitation and acquire a non-gap metabolic acidosis even as the initial perfusion deficit improves. In other cases, diarrhea or renal tubular dysfunction may be the primary acid-base disorder while shock is the overall clinical context.
Do not assume a normal gap means the situation is benign. It may simply mean the current problem is not increase of unmeasured acids. The bicarbonate can still be low, the pH can still be acidemic, and the patient can still have important organ stress. Always check the arterial blood gas, clinical trend, and response to resuscitation.
How Can Albumin Levels Affect Anion Gap Interpretation?
Low albumin can render the anion gap appear falsely normal or only mildly elevated. Albumin is a key unmeasured anion, so when it is low, the measured gap narrows even if clinically important acids are present. This is especially significant in critical illness, where low albumin is common and can get more info distort acid-base balance interpretation.
Correcting for albumin may help adjust the gap upward when albumin is low. That adjustment matters because an uncorrected result can miss a true high-gap process. In a patient with shock, this can postpone identification of lactic acidosis or another acid-base disorder that needs urgent attention.
Think about albumin correction when the result does not fit the patient’s condition. If the patient appears severely ill but the gap is “normal,” low albumin may be hiding the abnormality. Correcting for albumin gives a more accurate picture of acid-base balance and helps distinguish a genuine normal-gap state from a masked high-gap state.
In practice, albumin should be reviewed alongside the anion gap calculator result, the serum bicarbonate, and the arterial blood gas. That combined view is more reliable than any single number.
Which Other Labs Help Assess Shock and Acid-Base Status?
The anion gap is merely one piece of the acid-base assessment. During shock, several other labs help clarify the problem and support resuscitation. The key are lactate, arterial blood gas, base deficit, and serum ketones.
Lactate is particularly helpful because it reflects the severity of hypoperfusion and the degree of oxygen debt. An elevated lactate is consistent with lactic acidosis, though the exact source still requires clinical interpretation. The arterial blood gas reveals pH, PaCO2, and bicarbonate, helping identify whether the patient has a isolated metabolic acidosis or a mixed disorder with respiratory compensation. Base deficit offers another way to quantify metabolic acidosis and can help follow response over time. Serum ketones are important when ketoacidosis is possible.
Other supportive data may include creatinine, glucose, osmolar gap if toxic alcohols are a concern, and repeat electrolytes to follow the evolving serum chemistry. In critical care, a single snapshot is rarely enough. The broader lab pattern is the most reliable way to connect the anion gap to the actual cause of shock.
When Should You Recheck the Anion Gap in Shock?
Reassess the anion gap when the patient is receiving active resuscitation, when the cause of shock is still being worked out, or when treatment is underway and you need serial assessment. Serial monitoring is especially useful if the initial gap is elevated, if lactate is elevated, or if the clinical response is hard to interpret.
A falling gap can be a positive sign that the metabolic derangement is improving. In lactic acidosis, for example, the gap may fall as perfusion improves and oxygen delivery is improved. In ketoacidosis, it often narrows as insulin and fluids correct the metabolic process. In toxic ingestion, the pattern may evolve in another way, but trend monitoring still assists show whether treatment is effective.
Recheck sooner if the patient worsens, if new laboratory data do not match the bedside picture, or if a mixed disorder is suspected. In shock, the anion gap is most useful when it is paired with ongoing clinical assessment and a clear understanding of the compensatory response.
Common Pitfalls in Interpreting Anion Gap in Shock
A frequent mistake is lab error. A broken-down sample, sample mix-up, or outdated value can lead to faulty interpretation. Another pitfall is not identifying mixed acid base disorders, which are frequent in shock and can hide the true process.
Ignoring albumin correction is a common error. A low albumin can make a concerning high anion gap acidosis appear less obvious than it really is. The reverse can also occur: a patient can have both lactic acidosis and hyperchloremic acidosis, which may somewhat cancel out each other and create a artificially small gap.
The delta-gap is useful if a mixed acid-base disorder is suspected. It compares the change in anion gap with the change in bicarbonate and can show anion gap clinical significance whether there is an extra alkalosis or a different non-gap acidosis. This is valuable in undifferentiated shock, where more than one process may be happening at the same time.
Additional pitfalls include missing the patient context, not accounting for that shock itself may contribute to lactic acidosis, and depending on one isolated value rather than the full pattern. Accurate acid-base interpretation requires the electrolyte panel, arterial blood gas, lactate, and bedside hemodynamics to be read together.
FAQ: Anion Gap in Shock
What does a high anion gap mean in shock?
A high anion gap in shock usually means unmeasured acids are building up, usually from lactic acidosis due to tissue hypoperfusion. It can also reflect ketoacidosis, renal failure, toxic alcohols, or salicylates, so the result should be interpreted with the clinical picture and other labs.
Can shock cause a normal anion gap metabolic acidosis?
Yes. Shock can coexist with normal anion gap metabolic acidosis, especially if chloride-rich fluids are given during resuscitation or if there is another cause such as diarrhea or renal tubular acidosis. A normal gap does not exclude a significant acid-base disorder.
How does lactate affect the anion gap?
Lactate is an unmeasured anion, so when it rises it can increase the anion gap. Elevated lactate often reflects inadequate oxygen delivery, tissue hypoperfusion, or sepsis-related metabolic stress.
Why should albumin be considered when interpreting the anion gap?
Albumin is a major unmeasured anion. If albumin is low, the anion gap may appear artificially normal or only slightly elevated. Albumin correction helps uncover hidden metabolic acidosis, especially in critical illness.
What labs should be checked with an anion gap calculator in shock?
Along with the Anion Gap Calculator result, check lactate, arterial blood gas, base deficit, serum ketones, and repeat electrolytes including serum bicarbonate. These tests help define the acid-base disorder and distinguish lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and other causes.