What an Anion Gap Shows
The anion gap is a calculated value used in lab medicine to assess the difference between routinely measured cations and anions in electrolytes. In clinical practice, it helps physicians and lab professionals think about the balance of charged particles in blood and whether there are extra unmeasured anions present. This makes it a useful marker of electrolyte balance and broader acid-base status.
An Anion Gap Calculator is a fast diagnostic aid that converts common lab values into an interpretable number. The result does not diagnose a disorder by itself, but it provides important context to a patient’s serum chemistry and overall electrochemical balance. Because the anion gap reflects the relationship between positive and negative ions, it can reveal an underlying metabolic disturbance even when the rest of the panel seems only mildly abnormal.
From a physiology perspective, the anion gap is a window into buffer systems and acid accumulation. When acids accumulate, their anions may not be directly measured in a standard electrolyte panel. That is why the anion gap acts as a kind of anion difference—a practical measure that can point toward hidden biochemical changes.
In laboratory medicine, the value is best understood as part of a broader clinical interpretation. It complements, rather than replaces, history, exam findings, and other tests. Used correctly, it can help narrow a differential diagnosis and guide follow-up testing.
Anion Gap Formula and Required Inputs
The core calculation formula is simple. In most cases, the anion gap is calculated from sodium, chloride, and bicarbonate:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some labs report a somewhat different version if potassium is included, but the sodium-based formula is the most widely used in routine practice. An Anion Gap Calculator just applies this formula and returns a value that can be compared with the local interpretive range.
The necessary inputs come from the serum chemistry or chemistry analyzer output:
- Sodium: the main extracellular cation that is measured. Chloride: the main measured anion. Bicarbonate: usually reported as total CO2 on the chemistry panel, used as a bicarbonate proxy in many settings.
Because the result depends entirely on these three values, the https://blogfreely.net/budolfwboy/anion-gap-calculator-for-standard-laboratory-review-and-reading quality of the output depends on the quality of the input. A small error in any one test can shift the final number enough that it changes clinical interpretation. This is why understanding the underlying measurement method is significant in laboratory medicine.
A lot of users think of the result as a single number, but it is more helpful to view it as a reflection of the underlying serum chemistry and the patient’s current acid-base status. When the calculator output is unexpected, it is worth reviewing the original analytes before drawing conclusions.
How to Interpret a Standard, High, or Low Anion Gap
Analysis relies on the local reference range. Multiple laboratories may use varying analyzers, calibration approaches, and reporting conventions, so there is no universal “normal” value that fits all settings. The same numeric result may be interpreted differently depending on the platform and the institution’s reference range.
A within-range anion gap suggests that the measured electrolytes are in usual proportion and that there is no obvious increase in unmeasured anions. However, a normal value does not exclude disease. Some forms of metabolic acidosis occur with a normal anion gap, especially when bicarbonate loss is matched by chloride gain.
A high anion gap suggests that extra acids or negatively charged substances are present in the blood. This pattern is classically associated with high anion gap metabolic acidosis, where the extra acid is reflected in the increased gap. In contrast, a normal value in the setting of acidosis can point toward normal anion gap metabolic acidosis, which has a different set of causes and follow-up steps.
Albumin is one of the key modifiers of interpretation. Because albumin is a negatively charged protein, lower levels can reduce the apparent gap and mask clinically important acid-base changes. That means interpretation should always consider whether the measured number fits the patient’s broader clinical chemistry picture.
In practice, the result is best interpreted as part of the complete acid-base disorders assessment, not as a stand-alone answer. The same number can mean other things depending on whether the patient has symptoms, abnormal lactate, renal dysfunction, or other lab abnormalities.
Albumin Adjustment and Its Clinical Significance
Hypoalbuminemia is a common reason the measured anion gap can miss the true burden of unmeasured acids. Since serum albumin carries a negative charge, a decreased albumin concentration lowers the expected gap even when other acids are present. This is why many laboratory clinicians use a corrected anion gap.
The corrected result adjusts the observed value upward when albumin is low, making the estimate more clinically useful. In many workflows, albumin correction helps uncover a hidden metabolic acidosis that might otherwise appear minimal or even absent. The goal is not to force every result into a single interpretation, but to improve the accuracy of the corrected result when protein abnormalities are present.
Why this matters:
- It increases detection of acid-base abnormalities when serum albumin is reduced. It helps avoid underestimating high anion gap metabolic acidosis. It promotes better clinical interpretation in critically ill or hospitalized patients.
A calculator that includes albumin correction can be especially helpful because it turns a raw number into a more meaningful estimate of acid-base burden. In other words, the adjusted value can better reflect the patient’s actual electrolyte balance and the likely presence of unmeasured anions.
For laboratory medicine, the key point is that a single uncorrected number may be incomplete. When albumin is low, the Anion Gap Calculator should be used as a screening tool plus a beginning point for further assessment rather than the final word.
Typical Causes of an Elevated Anion Gap
An increased result often points to acid accumulation from excess organic or inorganic acids. The classic approach is high anion gap metabolic acidosis, but test interpretation should emphasize the actual cause rather than the pattern alone.
Three of the most common causes are lactic acidosis, ketoacidosis, and renal failure.
- Lactic acidosis: Increased lactate production or impaired clearance can increase the gap as lactate-associated anions accumulate. Ketoacidosis: Ketone bodies introduce unmeasured anions, often resulting in a clearly elevated gap. Renal failure: Decreased excretion of acid byproducts can lead to retention of unmeasured anions and a rising gap.
Other causes may also be present, but these three diagnoses are common anchor points in the differential diagnosis. In the laboratory context, the anion gap helps decide whether a patient’s metabolic disturbance is likely due to hidden acid retention or to another mechanism.
It is important to remember that an elevated gap is not itself a diagnosis. Instead, it is a clue that prompts additional testing, such as lactate, ketones, renal function markers, or toxicology studies when appropriate. The value becomes most useful when paired with other lab values and the clinical picture.
Causes of a Low Anion Gap
A decreased result is less common than a raised one, but it anion gap clinical significance can still be diagnostically important. The most common explanation is hypoalbuminemia, because a lowered albumin level depresses the expected number. If albumin is not considered, the result may look deceptively unremarkable or simply “off” without a clear reason.
Paraproteinemia is another significant cause. Certain abnormal proteins can alter the charge balance in blood and lower the measured gap. In some patients, this finding may be an initial sign that further evaluation of protein abnormalities is needed.
Laboratory error must also be considered. A low value may reflect a specimen issue, analyzer issue, or transcription problem rather than true physiology. That is why repeating the panel and reviewing the original serum chemistry is often the first useful step.
Other reasons can include interference with the measurement method or unusual shifts in electrolytes, but the three major causes above should be checked first. When the result is unexpectedly low, the best practice is to verify the numbers, review the patient’s albumin, and reassess whether the result aligns with the broader biochemical context.
Although clinicians often focus on elevated values, a low gap can reveal important pathology or analytical issues. In laboratory medicine, that makes it just as important to the overall interpretation process.
Practical Applications in Clinical Laboratory Practice
The anion gap has a important role in evaluating acid-base disorders. In routine laboratory medicine, it is commonly used alongside the arterial blood gas and the serum chemistry panel to help determine whether a patient has an acid-base problem and what type it may be.
Common uses include:
- Detecting a possible hidden metabolic problem when bicarbonate is low. Assisting in classifying metabolic acidosis as high gap or normal gap. Supporting the evaluation of unexplained electrolyte abnormalities. Serving as a quick screening tool before more specialized testing.
In a workflow setting, the calculator can link serum chemistry results with the broader acid-base picture. For example, a low bicarbonate on the chemistry panel plus an increased gap suggests acid retention rather than simple bicarbonate loss. That distinction matters because it changes the next diagnostic step.
The result also supports clinical interpretation when the arterial blood gas and chemistry panel do not seem to match perfectly. This can happen because of timing differences, sample handling, or different measurement platforms. The anion gap connects those data points and provides a practical way to interpret the patient’s acid-base status.
In practice, the calculator is more than arithmetic. It is a structured way to turn routine lab data into a more informative assessment of metabolic health.
Restrictions, Problems, and Effective Approaches
Even though the anion gap is helpful, it has important limitations. The main limitation is that the result varies with how the lab measures electrolytes. Modern analyzers often use ion-selective electrodes, and separate platforms can yield different numeric results. This means the same patient may have a different reported gap from one system to another.
Measurement error can also distort the answer. Small inaccuracies in sodium, chloride, or bicarbonate can shift the gap enough to change interpretation, especially when the result is near the reference range. Sample-handling issues, sample contamination, and analyzer interference should all be considered when the number seems inconsistent with the clinical picture.
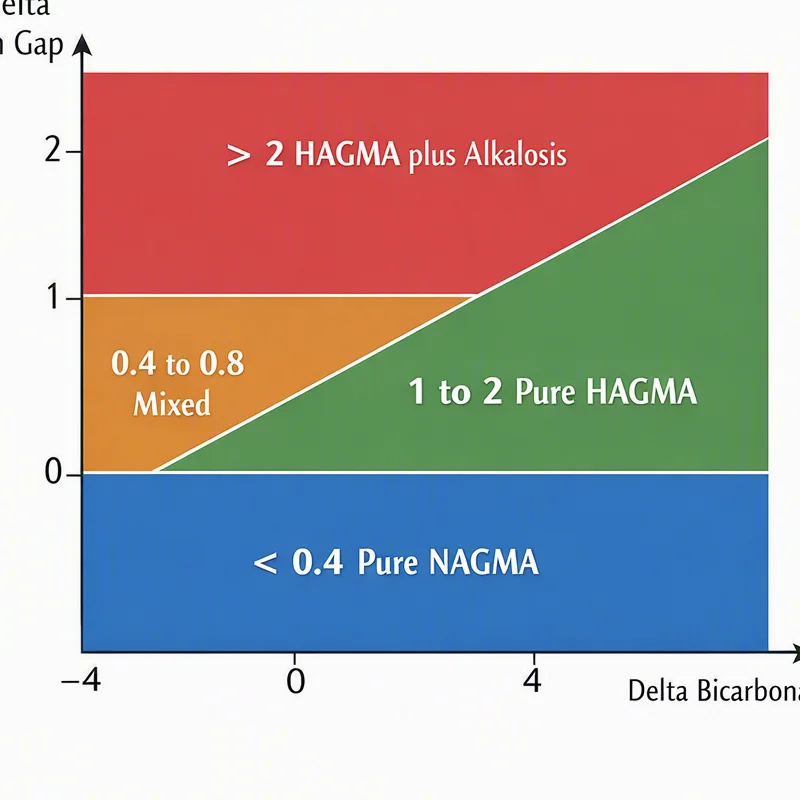
The delta gap is another useful concept in complex cases. It compares the change in the anion gap with the change in bicarbonate, helping to identify mixed acid-base disorders. In other words, it can show whether several process is affecting the patient at the same time. This is especially valuable when the raw number alone does not explain the overall pattern.
Good practice for using the calculator include:
- Confirm the inputs are from the same sample and the same time point when possible. Review the local reference range rather than assuming a universal normal value. Check serum albumin before final interpretation. Take into account ion-selective electrodes and platform differences when comparing results. Apply the delta gap when mixed disorders are suspected.
Above all, the anion gap should be interpreted as part of the overall acid-base disorders assessment. It is a valuable clue, not a standalone diagnosis. When used with the rest of the electrolyte panel and the clinical context, it becomes a practical tool for laboratory medicine.
FAQ on the Anion Gap Calculator
What does an Anion Gap Calculator used for?
An anion gap calculator is used to rapidly estimate the difference between reported cations and anions from routine lab values. It helps with interpretation of electrolyte data, assists assessment of metabolic acidosis, and can point to the presence of unmeasured anions. In laboratory medicine, it serves as a useful diagnostic aid rather than a final diagnosis.
How can you calculate the anion gap from lab values?
The usual calculation formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Many calculators use values from a standard electrolyte panel or serum chemistry report. The result should then be compared with the lab’s reference range for proper interpretation.
When should the anion gap be corrected for albumin?
Use albumin correction when serum albumin is low, especially in hypoalbuminemia. Low albumin can make the measured gap look falsely normal or low, so a corrected anion gap can provide a more accurate assessment of the patient’s acid-base state. This is particularly useful when evaluating suspected metabolic acidosis.
What can a high anion gap indicate?
A high value usually suggests high anion gap metabolic acidosis, meaning extra acids or other unmeasured anions are present. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted alongside the rest of the lab data and clinical findings to narrow the differential diagnosis.
Can a low anion gap be clinically significant?
Yes. A low result can point to hypoalbuminemia, paraproteinemia, or laboratory error. It may also reflect analytical or preanalytical issues affecting the measurement method. Even if less dramatic than a high value, a low result can still be an important clue in laboratory medicine and should not be ignored.