What an Anion Gap Calculator Calculates
An anion gap is a calculated value that assists in evaluating electrolytes and spot signs of metabolic acidosis. An Anion Gap Calculator takes in routine laboratory values to approximate the difference between commonly measured ions and the unmeasured negatively charged ions in the blood. This turns it a practical initial check for spotting an acid-base disorder that may not be obvious from symptoms alone.
In a typical serum chemistry panel, the calculation looks at the ratio between positively charged and negatively charged particles. The result reflects the body’s acid-base balance and can point toward an electrolyte imbalance, a metabolic derangement, or another cause of acid buildup. Because the anion gap is influenced by measured ions as well as unmeasured anions, it is often used as part of broader diagnostic support rather than as a stand-alone answer.
Clinically, the anion gap is most helpful when a patient’s laboratory values suggest acidosis. A widened gap can indicate accumulation of acids such as lactate or ketones, while a normal result can suggest a different type of problem. The calculator gives a fast way to translate raw numbers into meaningful clinical interpretation, especially when paired with the patient’s symptoms and other laboratory values.
The anion gap is not a diagnosis by itself; it is a clue that helps narrow the differential diagnosis.How Venous Blood Gas Is Used
A venous blood gas is usually enough for reviewing many acid-base concerns because it offers valuable information about pH, bicarbonate, and pCO2. Though an arterial blood gas still matters in some settings, venous sampling is often used when the goal is to assess metabolic status and determine the presence of metabolic acidosis.
For anion gap calculation, the key inputs are generally part of a chemistry panel rather than the gas sample itself. Nevertheless, venous blood gas results add important physiologic context. If the pH is low and bicarbonate is reduced, the anion gap can help determine whether the cause is a high anion gap metabolic acidosis or a process with a normal gap. The pCO2 is also useful because it helps show whether respiratory compensation is occurring appropriately.
Venous blood gas analysis is especially valuable because it is fast, low in invasiveness, and often easier to obtain than arterial sampling. In practice, the calculator works best when venous gas data are interpreted alongside the serum chemistry panel. Together, these results provide a more complete picture of the patient’s acid-base disorder and overall buffer system status.
Anion Gap Equation
The standard calculation formula for the anion gap relies on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
Some tools also use potassium in the equation:
Anion gap = (sodium + potassium) - (chloride + bicarbonate)
Each version estimate the difference between measured cations and measured anions. The version without potassium is used more often because potassium is a smaller contributor to the gap in many routine clinical settings. The calculator’s goal is to identify an anion deficit or increase that may reflect unmeasured acids in the circulation.
For the most accurate results, use values from the same time period and the same lab system when possible. The inputs should come from a reliable electrolyte panel and should match the values used in the patient’s blood gas analysis. A small mismatch between panels can affect result interpretation, especially when the anion gap is only mildly abnormal.
Typical calculator inputs include:
- Sodium Chloride Bicarbonate Potassium, if the formula includes it
Because the result is derived from routine laboratory values, the calculator is a convenient tool for fast point-of-care assessment and broader clinical review.
How to Understand a Typical, Raised, or Low Anion Gap
A standard anion gap indicates that the drop in bicarbonate is being offset by an rise in chloride. This pattern is often called normal anion gap metabolic acidosis, also known as chloride-rich acidosis. In this setting, the problem is usually related to bicarbonate depletion or impaired acid handling rather than a increase of unmeasured acids.
A raised anion gap metabolic acidosis means that unmeasured acids are building up. This is the pattern clinicians watch for when evaluating metabolic acidosis from causes such as lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or uremia. The greater the gap, the more clearly it suggests the presence of additional unmeasured anions.
A decreased anion gap is rarer but still important. It can be caused by decreased albumin, laboratory variation, or unusual conditions that alter the relationship between measured ions and unmeasured anions. A markedly low result should not be dismissed, especially if the clinical picture suggests another issue.
Reading the result always requires the overall clinical picture. A single number cannot explain the full story about an acid-base disorder. The best use of the calculator is as a decision aid that improves result interpretation when combined with pH, pCO2, bicarbonate, and symptoms.
Albumin Correction and Clinical Considerations
Albumin serves as one of the main unmeasured anions in blood, so reduced albumin can make the anion gap appear incorrectly normal. That is why hypoalbuminemia plays such a big role when using an Anion Gap Calculator. If albumin is reduced, the measured anion gap may downplay the presence of an underlying acid load.
An albumin-corrected anion gap modifies the raw result using a correction factor based on the albumin level. This helps reveal hidden gaps that might otherwise be missed. The correction is particularly useful when evaluating suspected lactic acidosis, ketoacidosis, or mixed disorders in patients with low albumin.
For example, a patient with low albumin may have a borderline anion gap even though the true burden of unmeasured anions is substantial. Correcting for albumin can strengthen clinical judgment and clarify the differential diagnosis. However, the corrected result still must be interpreted in the context of the full presentation.
Important caveats include:
- Albumin can alter the expected reference range for the anion gap. Correction enhances sensitivity for hidden metabolic derangement. The corrected number does not eliminate the need for clinical interpretation.
Common Causes of Elevated Anion Gap
A high anion gap usually means there are extra acids in the system. The most common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and uremia. Each cause raises the concentration of unmeasured anions and moves the balance away from normal acid-base balance.
Lactic acidosis occurs when lactate builds up, often due to tissue hypoperfusion, severe illness, or impaired oxygen delivery. Ketoacidosis appears when ketone bodies accumulate, which can happen in diabetes, starvation, or alcohol-related metabolic states. Both produce a high anion gap metabolic acidosis.
Renal failure leads to retention of acids that the kidneys normally eliminate, while uremia reflects the buildup of uremic acids and other retained solutes. Toxic alcohols such as methanol or ethylene glycol can also create a marked gap by generating organic acids after metabolism.
Because these conditions can look similar on the calculator, the anion gap should be viewed as a screening tool, not a final answer. The next step is to match the lab pattern to the patient’s symptoms, history, and other laboratory results.
Limitations With Venous Blood Gas Values
Even though a venous blood gas is valuable, it does not fully replace an arterial blood gas in every situation. Venous pH and pCO2 are useful for trending and for general acid-base assessment, but they may not reflect oxygenation status the way an arterial sample does. Thus, the choice of test should reflect the clinical question.
There is a risk of sampling error. When the blood draw is delayed, contaminated, or not matched with the chemistry panel, the calculator result may be misleading. Slight discrepancies between anion gap clinical significance specimens can matter when the anion gap is near the upper end of the reference range.
Laboratory variation is another important limitation. Different analyzers can produce slightly different sodium, chloride, or bicarbonate values, which changes the final result. That is why the same patient may have modestly different anion gap values across institutions or even between testing platforms.
In the end, the anion gap should never be read outside its clinical context. A normal result does not exclude all metabolic problems, and a high result does not specify the exact cause. It is one piece of a larger diagnostic picture, supported by blood gas analysis, examination, and targeted testing.
Stepwise Example Calculation
This is a simple worked example based on a standard chemistry panel and venous blood gas data. Suppose the electrolyte panel displays:
- Sodium: 140 Chloride: 100 Bicarbonate: 16
Using the usual formula:
Anion gap = 140 - (100 + 16) = 24
If potassium also be added and the level is 4.0, the formula becomes:
Anion gap = (140 + 4) - (100 + 16) = 28
Now add the venous blood gas values. If the venous pH is low and pCO2 is also reduced, that supports a primary metabolic process with respiratory compensation. A bicarbonate of 16 and an elevated anion gap together suggest high-gap metabolic acidosis.
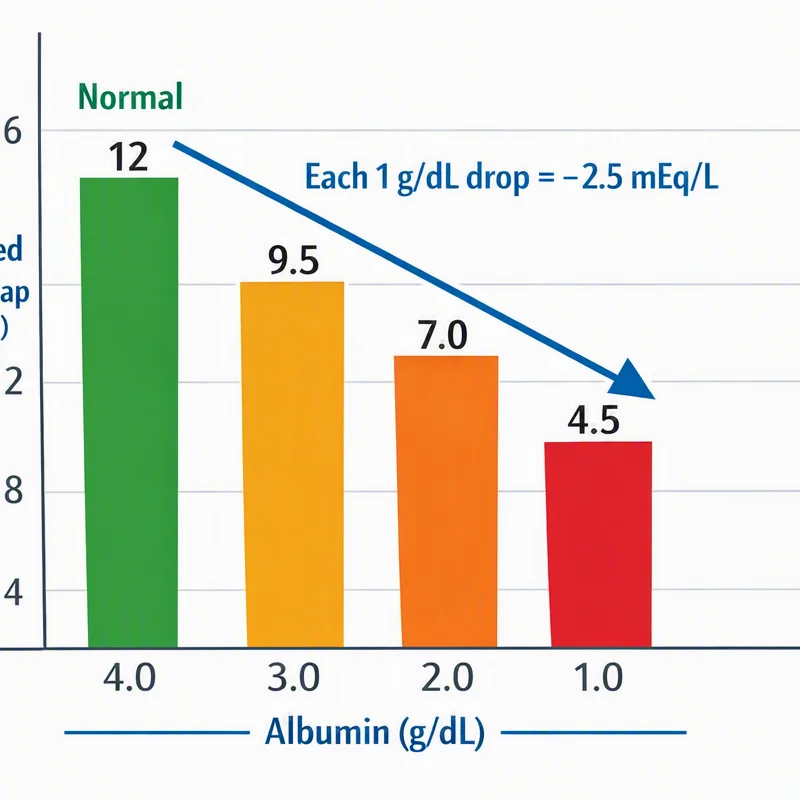
Afterward, consider albumin. Should albumin is low, the raw number may underestimate the true gap. After applying correction for albumin, the result may move even higher, heightening suspicion for hidden acids such as lactate or ketones. That is how the calculator supports interpretation rather than replacing it.
Reference range matters as well. When lab’s methanol high anion gap expected range is 8 to 12, then a result of 24 is clearly elevated. If the value is only slightly above the range, the full picture becomes even more important, including symptoms, medications, and the rest of the laboratory profile.
Common Questions
How do you calculate an anion gap from venous blood gas results?
The anion gap is usually calculated from the electrolyte panel, not directly from the venous blood gas. You use sodium, chloride, and bicarbonate in the formula, then interpret the result alongside venous pH and pCO2. The Anion Gap Calculator helps combine these values into a more complete picture of acid-base status.
Can venous blood gas replace arterial blood gas for anion gap interpretation?
In many situations, yes. A VBG gives valuable information about pH, bicarbonate, and pCO2 for evaluating metabolic problems. However, an arterial gas may still be needed when oxygenation or precise respiratory assessment is important.
When should the anion gap be corrected for albumin?
Correct the gap when albumin is low or thought to be low, notably if the raw anion gap seems within range despite signs of acid buildup. Hypoalbuminemia can conceal a true elevation, so the albumin-corrected anion gap offers better clinical support.
What does a high anion gap mean on a venous blood gas?
A elevated result usually suggests high anion gap metabolic acidosis, which can be caused by lactic acidosis, ketoacidosis, renal failure, toxic alcohols, or uremia. The finding should be interpreted with the venous pH, pCO2, and the broader clinical picture.
What are the limitations of an anion gap calculator?
An anion gap calculator depends on accurate laboratory values, so sampling error and laboratory variation can influence the result. It also does not identify the exact cause of the abnormality. It works best as a screening tool within a broader clinical interpretation of the patient’s acid-base disorder.