An anion gap calculator is more informative than a simple math tool when you need rapid, precise diagnostic interpretation of serum electrolytes. In clinical practice, the anion gap helps clinicians analyze acid-base balance, look for metabolic acidosis, and refine a broad differential diagnosis by distinguishing likely causes of unmeasured anions from disorders driven by direct bicarbonate loss or chloride retention. If used correctly, it becomes part of a broader diagnostic algorithm rather than a stand-alone result.
This guide describes how the anion gap formula works, how to interpret a normal anion gap versus an elevated anion gap, and how to correct for hypoalbuminemia using albumin correction. It also shows how to connect the result to real-world causes such as lactic acidosis, ketoacidosis, renal failure, renal tubular acidosis, and toxic alcohol ingestion.
What the Anion Gap Measures
The anion gap is a computed value based on common electrolytes on a basic metabolic panel. It estimates the difference between measured positively charged ions and measured negatively charged ions, aiding clinicians identify the presence of unmeasured anions in the blood. Because the body maintains tight acid-base balance through buffer systems and kidney function, shifts in the gap can indicate a meaningful metabolic derangement.
In the classic interpretation, sodium is compared against chloride and bicarbonate, which are the main contributors in routine chemistry testing. The gap reflects the balance between these measured ions and other charged particles not directly reported, such as proteins, phosphate, sulfate, lactate, and organic acids. This is why the gap can detect a hidden acid-base disorder even before the precise cause is known.
The test is often used as part of clinical assessment when a patient presents with low bicarbonate, altered mental status, unexplained tachypnea, or an abnormal metabolic profile. A single number does not confirm the diagnosis, but it can quickly steer attention toward the right branch of the differential diagnosis.
Formula for Anion Gap and Input Values
The basic anion gap equation is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some clinicians include potassium in the equation, especially in older textbooks or some calculation approaches:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Modern medical use emphasizes the sodium-based version because potassium is usually low in relation to sodium and offers minimal benefit to routine interpretation. Still, an anion gap calculator may use either approach, so it is important to know which formula is being applied. Small differences in the equation can shift the number enough to affect clinical judgment.
Key inputs are drawn from the electrolyte panel or chemistry panel: sodium, chloride, and bicarbonate. In many cases, the calculator also asks for albumin because low protein levels can mask a clinically important elevation. Since serum albumin level strongly influences the baseline gap, a raw number without context can be misleading.
For instance, a patient with sodium 140, chloride 104, and bicarbonate 24 has an anion gap of 12. That value may be normal depending on the lab’s reference range, but the interpretation changes if the patient has severe hypoalbuminemia or evidence of metabolic acidosis. The calculation is only the starting point for clinical interpretation.
How to Understand a Normal vs Increased Anion Gap
Interpretation starts from the lab’s reference range, since typical readings vary slightly by assay and institution. In general, a normal anion gap indicates that the bicarbonate decrease is being balanced by a rise in chloride, while an elevated anion gap implies accumulation of unmeasured acids or their anions. Either pattern can indicate metabolic acidosis, but they reflect different etiologies.
A high anion gap metabolic acidosis usually means acid is being added to the body or retained because the kidneys cannot clear it effectively. Common causes include organic acids and toxins. By contrast, a normal anion gap metabolic acidosis is often a hyperchloremic process, where bicarbonate is lost and chloride rises to maintain electroneutrality.
Practical interpretation works best as a branching diagnostic algorithm:
- Normal anion gap: think bicarbonate loss or renal acid-handling problems. Elevated anion gap: think added acids, accumulation of acids, or toxin exposure. If the number seems unexpectedly normal, check albumin and consider anion gap correction.
It is important as well to confirm whether the patient truly has metabolic acidosis. A low bicarbonate on a chemistry panel is not enough by itself; an arterial blood gas can help clarify pH and breathing compensation. This is especially useful when mixed acid-base disorders are possible.
Adjusted Anion Gap for Hypoalbuminemia
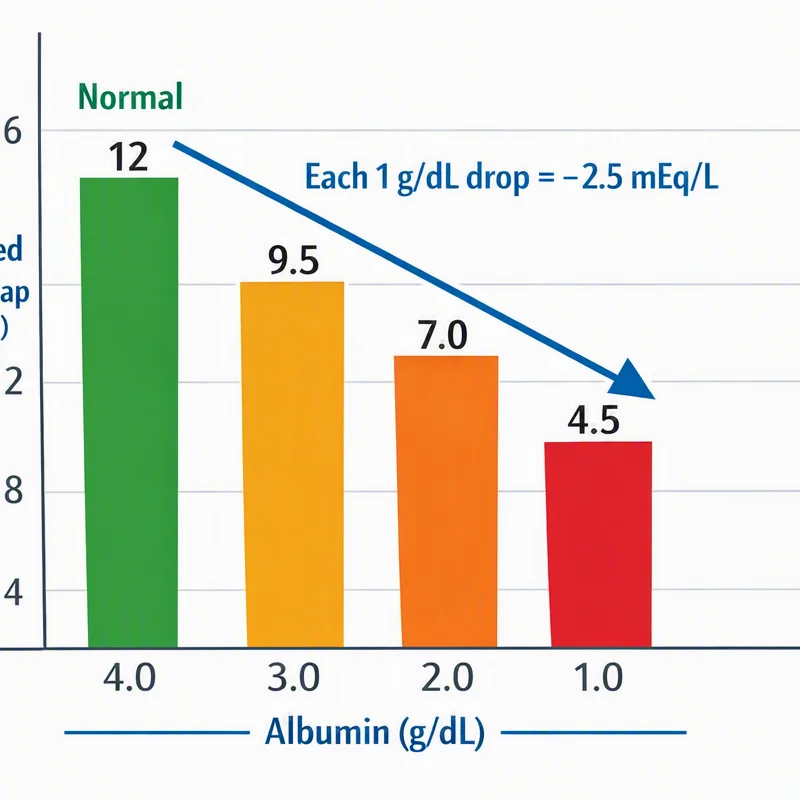
Albumin is a major unmeasured anion, so low albumin decreases the apparent anion gap. That means a patient with hypoalbuminemia may have a deceptively unchanged or only slightly elevated result despite clinically significant acidosis. This is why albumin correction is important in routine interpretation.
The corrected anion gap adjusts the measured value upward when serum albumin is below normal. Several correction methods are available, but a common clinical approach is to add a fixed amount for each gram per deciliter albumin is below normal. The exact factor may change by institution, so the calculator should be used in line with local practice or its stated assumptions.
This anion gap correction is especially important in severely ill patients, patients with malnutrition, liver disease, chronic inflammation, or nephrotic states. In these settings, the raw number may diminish the burden of unmeasured anions and therefore obscure a true acid-base disorder.
Consider this clinical logic: a patient has low bicarbonate and a “normal” gap, but the serum albumin level is markedly reduced. After albumin correction, the gap becomes elevated, revealing a mixed picture or a hidden high-gap process. In other words, the corrected number can shift the differential diagnosis and the speed of workup.
Diagnostic Approach of high anion-gap metabolic acidosis
High anion gap metabolic acidosis occurs when acids gather or are retained. The core idea is that bicarbonate is used up while the associated anions are not detected in the standard panel. The outcome is a widened gap and a focused differential.
Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one has typical clinical clues, but similarity is common, so the anion gap should be integrated with medical history, exam, and lab values.
- Lactic acidosis: frequently linked to hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Ketoacidosis: encompasses starvation ketosis, alcoholic ketosis, and diabetic ketoacidosis, which often presents with hyperglycemia, dehydration, and ketones. Renal failure: impaired acid excretion leads to accumulation of acids and gradual metabolic derangement. Toxic alcohol ingestion: including methanol or ethylene glycol, which can lead to severe high-gap acidosis and end-organ injury.
Within diabetic ketoacidosis, the gap is commonly markedly elevated because ketone bodies build up. Within renal failure, the pattern may evolve with progressive retained acids and a decline in renal function. In cases of toxic alcohol intake, the anion gap can increase early, and the clinical picture may include osmolar gap shifts, visual symptoms, neurologic impairment, or kidney injury depending on the agent.
By using an anion gap calculator here helps prioritize the next move in clinical evaluation: lactate testing, ketone assessment, toxicology review, or renal assessment. The number does not replace judgment, but it sharpens the differential assessment.
Differential Assessment of Normal Anion Gap Metabolic Acidosis
A normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. In this case, the issue is usually not the addition of unmeasured acid, but rather bicarbonate loss or impaired renal acid handling. The anion gap remains normal because chloride substitutes for the lost bicarbonate.
Major causes include diarrhea and renal tubular acidosis. Gastrointestinal bicarbonate loss is a classic mechanism in diarrhea, especially when losses are prolonged or severe. The kidneys may also fail to acidify urine properly in renal tubular acidosis, producing a chronic or recurrent normal-gap acidosis.
Other contributors to normal anion gap metabolic acidosis can include high-volume saline administration, certain medications, and tubular dysfunction, but the main clinical distinction remains the same: chloride increases as bicarbonate falls. This explains why the serum chemistry pattern matters as much as the calculated number.
If you see a normal-gap pattern, ask how to interpret AG whether the problem is a true loss of alkali. If the answer is yes, then loss of bicarbonate from the gut or kidney becomes central to the diagnostic workup. That makes the anion gap an efficient tool for directing the next branch of the acid-base differential diagnosis.
Frequent Interpretation Issues and Medical Setting
Even when a careful calculation can mislead if the medical situation is ignored. One common issue is lab error, such as contaminated specimen, data entry error, or a mismatched set of results. Before assuming that a major acid base problem exists, confirm that the lab values are self-consistent and consistent with the patient’s condition.
Another mistake is neglecting albumin. If the protein concentration is decreased, the raw anion gap may underestimate the true burden of unmeasured anions. That is why albumin correction should be taken into account in any patient with suspected metabolic acidosis and low albumin.
The delta gap is an important important concept. When the anion gap is raised, the delta gap relates the rise in the gap to the fall in bicarbonate. This helps detect mixed acid-base disorders, such as coexisting metabolic alkalosis or an additional normal-gap acidosis. In practice, the delta gap can indicate whether the patient’s metabolic profile is more complex than the first calculation suggests.
Other common common pitfalls include using the improper reference range, failing to check pH on an arterial blood gas, and interpreting a single number without considering respiratory compensation. The most accurate results come from integrating the calculator output with a full clinical assessment and the broader picture of electrolyte imbalance and organ function.
When You Should Use an Anion Gap Calculator in Clinical Workflow
An anion gap calculator is especially useful early in the evaluation of suspected acid-base disorder. It fits naturally into a workflow that begins with a basic metabolic panel or electrolyte panel, then progresses to an arterial blood gas when pH and compensation need clarification. This sequence promotes efficient clinical decision support and more focused testing.
Use the calculator if bicarbonate is decreased, when there is unexplained tachypnea or altered mental status, or when toxin exposure is suspected, sepsis, renal dysfunction, or ketoacidosis. It is also useful when reviewing serial labs because changes in the anion gap can track improvement or advancement in the underlying metabolic derangement.
In practical terms, the workflow often looks like this:
- Examine the basic metabolic panel for sodium, chloride, and bicarbonate. Run the anion gap calculation using the calculator. Check albumin and apply corrected anion gap logic if needed. Use an arterial blood gas to confirm acidemia or alkalemia and assess compensation. Branch to the appropriate differential diagnosis for high-gap or normal-gap causes.
This approach makes the calculator part of a broader clinical decision-making process rather than a standalone number generator. It helps clinicians move quickly from a chemistry abnormality to a meaningful explanation, especially in high-acuity settings.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is used to determine the difference between measured cations and anions on a chemistry panel. Clinically, it helps recognize metabolic acidosis, guide acid-base differential diagnosis, and distinguish between high-gap and normal-gap causes of acid-base disorders. It is especially helpful when combined with albumin and arterial blood gas data.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some methods also add potassium, but the sodium-based formula is most commonly used. The values usually come from a basic metabolic panel or related electrolyte panel.
Why does low albumin affect the anion gap?
Albumin is a key unmeasured anion, so when hypoalbuminemia is present, the measured gap can seem lower than it truly is. That is why albumin correction is important. A corrected anion gap gives a better picture of the real burden of unmeasured acids and strengthens diagnostic interpretation.
What leads to a high anion gap metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions elevate unmeasured acids or impair acid clearance, widening the gap and indicating a significant metabolic problem.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A patient can have normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern often occurs with diarrhea or renal tubular acidosis, where bicarbonate loss is matched by a rise in chloride. In that setting, the gap stays normal even though true acidosis is present.