An anion gap calculator is more informative than a simple calculation tool when you need rapid, reliable diagnostic interpretation of serum electrolytes. In real-world use, the anion gap helps clinicians evaluate acid-base balance, check for metabolic acidosis, and refine a broad differential diagnosis by distinguishing likely causes of unmeasured anions from disorders driven by direct bicarbonate loss or chloride retention. When used properly, it becomes part of a broader diagnostic algorithm rather than a stand-alone result.
This guide describes how the anion gap formula works, how to interpret a normal anion gap versus an elevated anion gap, and how to correct for hypoalbuminemia using albumin correction. It also shows how to connect the result to real-world causes such as lactic acidosis, ketoacidosis, renal failure, renal tubular acidosis, and toxic alcohol ingestion.
How the Anion Gap Measures
The anion gap is a calculated value based on common electrolytes on a basic metabolic panel. It estimates the difference between measured positively charged ions and measured negatively charged ions, aiding clinicians detect the presence of unmeasured anions in the blood. Since the body maintains tight acid-base balance through buffer systems and kidney function, shifts in the gap can signal a significant metabolic derangement.
In the classic interpretation, sodium is compared against chloride and bicarbonate, which are the main contributors in routine chemistry testing. The gap shows the balance between these measured ions and other charged particles not directly reported, such as proteins, phosphate, sulfate, lactate, and organic acids. This is why the gap can detect a hidden acid-base disorder even before the precise cause is known.
The test is often used as part of clinical assessment when a patient presents with low bicarbonate, altered mental status, unexplained tachypnea, or an abnormal metabolic profile. A single number does not confirm the diagnosis, but it can quickly direct attention toward the right branch of the differential diagnosis.
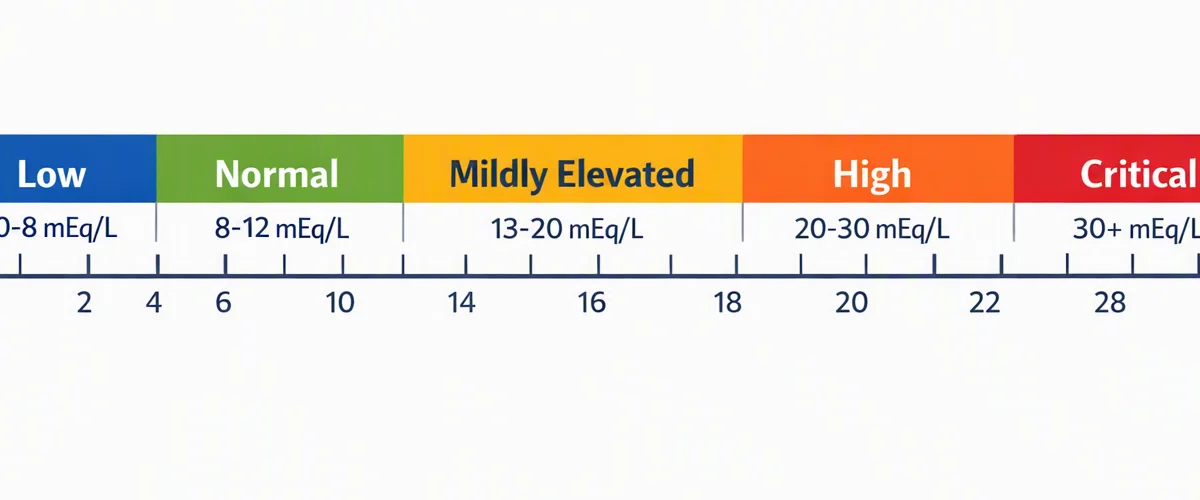
Formula for Anion Gap and Input Values
The standard anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain clinicians use potassium in the formula, notably in older textbooks or certain calculation methods:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Most modern clinical use focuses on the sodium-based version because potassium is usually low in relation to sodium and contributes little value to routine interpretation. However, an anion gap calculator may use either approach, so it is important to know which formula is being applied. Small differences in the equation can shift the number enough to affect clinical judgment.
The main inputs are drawn from the electrolyte panel or chemistry panel: sodium, chloride, and bicarbonate. In many cases, the calculator also asks for albumin because low protein levels can mask a clinically important elevation. Since serum albumin level strongly influences the baseline gap, a raw number without context can be misleading.
As an example, a patient with sodium 140, chloride 104, and bicarbonate 24 has an anion gap of 12. That value may be normal depending on the lab’s reference range, but the interpretation changes if the patient has severe hypoalbuminemia or evidence of metabolic acidosis. The calculation is only the starting point for result interpretation.
Interpreting a Typical vs Increased Anion Gap
Interpretation starts with the lab’s reference range, since typical readings change slightly by assay and institution. In general, a normal anion gap implies that the bicarbonate decrease is being offset by a rise in chloride, while an elevated anion gap implies accumulation of unmeasured acids or their anions. Both patterns can indicate metabolic acidosis, but they reflect different etiologies.
A high anion gap metabolic acidosis usually means acid is being added to the body or retained because the kidneys cannot clear it effectively. Common causes include organic acids and toxins. By contrast, a normal anion gap metabolic acidosis is often a hyperchloremic process, where bicarbonate is lost and chloride rises to maintain electroneutrality.
Practical interpretation works best as a branching diagnostic algorithm:
- Normal anion gap: think bicarbonate loss or renal acid-handling problems. Elevated anion gap: think added acids, accumulation of acids, or toxin exposure. If the number seems unexpectedly normal, check albumin and consider anion gap correction.
It is important as well to confirm whether the patient truly has metabolic acidosis. Low bicarbonate levels on a chemistry panel is not sufficient on its own; an arterial blood gas can help clarify pH and breathing compensation. This is particularly helpful when mixed acid-base disorders are possible.
Revised Anion Gap for Hypoalbuminemia
Albumin is a key not directly measured anion, so low albumin decreases the observed anion gap. That means a patient with hypoalbuminemia may have a deceptively normal or only mildly elevated result despite important acidosis. This is why albumin correction matters in everyday interpretation.
The corrected anion gap modifies the measured value upward when serum albumin is below normal. Several correction methods are available, but a common clinical approach is to add a fixed amount for each gram per deciliter albumin is below normal. The exact factor may change by institution, so the calculator should be used in line with local practice or its stated assumptions.
This anion gap correction is especially important in unstable patients, patients with malnutrition, liver disease, chronic inflammation, or nephrotic states. In these settings, the raw number may diminish the burden of unmeasured anions and therefore hide a true acid-base disorder.
Consider this clinical logic: a patient has low bicarbonate and a “normal” gap, but the serum albumin level is markedly reduced. After albumin correction, the gap becomes elevated, revealing a mixed picture or a hidden high-gap process. In other words, the corrected number can alter the differential diagnosis and the priority of workup.
Differential Diagnosis of high anion gap metabolic acidosis
High anion gap metabolic acidosis occurs when acids accumulate or are retained. The core idea is that bicarbonate is consumed while the associated anions are not measured in the standard panel. The result is a broadened gap and a structured differential.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each one has characteristic clinical clues, but similarity is common, so the anion gap should be interpreted together with patient history, exam, and lab values.
- Lactic acidosis: often related to hypoperfusion, sepsis, hypoxemia, or severe metabolic stress. Ketoacidosis: covers starvation ketosis, alcoholic ketosis, and diabetic ketoacidosis, which commonly presents with hyperglycemia, dehydration, and ketones. Renal failure: decreased acid excretion leads to accumulation of acids and progressive metabolic derangement. Toxic alcohol ingestion: including methanol or ethylene glycol, which can lead to severe high-gap acidosis and end-organ injury.
In DKA, the gap is often greatly elevated because ketone bodies pile up. Within renal failure, the pattern may progress with worsening retained acids and a reduction in renal clearance. With toxic alcohol intake, the anion gap can rise early, and the clinical picture may include osmolar gap alterations, visual symptoms, neurologic deterioration, or kidney injury depending on the agent.
Using an anion gap calculator in this setting helps determine the next move in medical assessment: lactate testing, ketone testing, toxicology evaluation, or kidney function review. The value doesn’t replace judgment, but it sharpens the differential diagnosis.
Differential Assessment of normal anion gap metabolic acidosis
A normal anion gap metabolic acidosis is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. In this case, the issue is usually not the addition of unmeasured acid, but rather bicarbonate loss or impaired renal acid handling. The anion gap remains normal because chloride substitutes for the lost bicarbonate.
Common causes include diarrhea and renal tubular acidosis. Gastrointestinal bicarbonate loss is a classic mechanism in diarrhea, especially when losses are prolonged or severe. The kidneys may also fail to acidify urine properly in renal tubular acidosis, producing a chronic or recurrent normal-gap acidosis.
Other causes of normal anion gap metabolic acidosis can include high-volume saline administration, certain medications, and tubular dysfunction, but the main clinical distinction remains the same: chloride increases as bicarbonate falls. This is why the serum chemistry pattern matters as much as the calculated number.
When evaluating a normal-gap pattern, ask whether the problem is a true loss of alkali. If the answer is yes, then loss of bicarbonate from the gut or kidney becomes central to the diagnostic workup. That makes the anion gap an efficient tool for directing the next branch of the acid-base differential diagnosis.
Common Interpretation Errors and Medical Background
Even when a precise result can be misleading if the medical setting is ignored. One common issue is lab error, such as sample contamination, recording error, or a mismatched set of results. Prior to assuming that a dramatic acid base problem exists, confirm that the https://anion-gap-reader143.image-perth.org/how-to-work-with-an-anion-gap-calculator-for-blood-gas-analysis lab values are internally consistent and consistent with the patient’s condition.
A further pitfall is neglecting albumin. If the albumin level is decreased, the raw anion gap may underestimate the true burden of unmeasured anions. This is why albumin correction should be taken into account in any patient with suspected metabolic acidosis and low albumin.
The delta gap is an important important concept. When the anion gap is elevated, the delta gap contrasts the rise in the gap to the fall in bicarbonate. This assists in detect mixed acid-base disorders, such as concurrent metabolic alkalosis or an additional normal-gap acidosis. In practice, the delta gap can show whether the patient’s metabolic profile is more complex than the first calculation suggests.
Other common mistakes include using the wrong reference range, failing to confirm pH on an arterial blood gas, and interpreting a single number without considering respiratory compensation. The best results come from integrating the calculator output with a full clinical assessment and the broader picture of electrolyte imbalance and organ function.
When You Should Use an Anion Gap Calculator in Clinical Workflow
An anion gap calculator is especially useful early in the evaluation of suspected acid-base disorder. It fits naturally into a workflow that begins with a basic metabolic panel or electrolyte panel, then expands to an arterial blood gas when pH and compensation need clarification. This sequence enables efficient clinical decision support and more focused testing.
Use the calculator if bicarbonate is decreased, when unexplained tachypnea is present or altered mental status, or when there is concern for toxin exposure, sepsis, renal dysfunction, or ketoacidosis. It is also useful during serial lab review because changes in the anion gap can track improvement or advancement in the underlying metabolic derangement.
In practical terms, the workflow often looks like this:
- Check the basic metabolic panel for sodium, chloride, and bicarbonate. Use the anion gap calculation using the calculator. Measure albumin and apply corrected anion gap logic if needed. Order an arterial blood gas to confirm acidemia or alkalemia and assess compensation. Branch to the appropriate differential diagnosis for high-gap or normal-gap causes.
This approach makes the calculator part of a larger clinical decision-making process rather than a standalone number generator. It helps clinicians advance efficiently from a chemistry abnormality to a meaningful explanation, especially in high-acuity settings.
FAQ About Anion Gap Interpretation
What is an anion gap calculator used for?
An anion gap calculator is used to calculate the difference between measured cations and anions on a chemistry panel. Clinically, it helps identify metabolic acidosis, support acid-base differential diagnosis, and differentiate between high-gap and normal-gap causes of acid-base disorders. It is especially helpful when combined with albumin and arterial blood gas data.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some methods also add potassium, but the sodium-based formula is most commonly used. The values usually come from a basic metabolic panel or related electrolyte panel.
Why does low albumin affect the anion gap?
Albumin is a key unmeasured anion, so when hypoalbuminemia is present, the measured gap can appear lower than it truly is. That is why albumin correction is important. A corrected anion gap more accurately reflects the real burden of unmeasured acids and enhances diagnostic interpretation.
What leads to a high anion gap metabolic acidosis?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, diabetic ketoacidosis, renal failure, and toxic alcohol ingestion. These conditions elevate unmeasured acids or decrease acid clearance, expanding the gap and indicating a significant metabolic problem.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A patient can have normal anion gap metabolic acidosis, also called hyperchloremic acidosis. This pattern often occurs with diarrhea or renal tubular acidosis, where bicarbonate loss is matched by a rise in chloride. In that setting, the gap stays normal even though true acidosis is present.